Antibiotics for Water Infection UK: A Practical Guide
Antibiotics for water infection UK explained clearly. Compare nitrofurantoin, trimethoprim and pivmecillinam with NHS-aligned advice.

A child wakes you at 2am, or you're the one making another painful trip to the loo. Burning, urgency and passing only a little urine can make a simple bladder infection feel overwhelming. In the UK, antibiotics for a water infection usually means treatment for cystitis, a lower urinary tract infection. The right medicine depends on your symptoms, pregnancy status, sex, age, recent antibiotics and kidney function. This guide explains the main NHS choices, why nitrofurantoin often comes first, when trimethoprim or pivmecillinam may suit better, how Pharmacy First and online prescribing fit in, and which warning signs need urgent help.
Five key takeaways
- Cystitis affects the bladder: Burning, urgency and frequent urination often point to a lower UTI.
- Nitrofurantoin is often first choice: NICE recommends it for suitable non-pregnant adults with adequate kidney function.[1]
- Resistance changes the decision: Trimethoprim resistance is much higher than nitrofurantoin resistance in UK surveillance.[1][2]
- Some groups need a different pathway: Men, pregnant women, children and people with recurrent symptoms may need testing and review.
- Red flags need prompt care: Fever, flank pain, vomiting, confusion or visible blood can signal a more serious problem.
What a water infection is and why antibiotics matter
A water infection is the everyday name many people use for a urinary tract infection, or UTI. Cystitis affects the bladder and is called a lower UTI. Typical symptoms include burning when you pass urine, needing the toilet often, sudden urgency and discomfort low in the abdomen.
Most adult women under 65 who aren't pregnant, don't have a catheter and don't have known kidney problems have an uncomplicated lower UTI. A complicated infection needs more care because another factor may alter the diagnosis, antibiotic choice or risk of complications.
When antibiotics usually matter
Bacteria, most often E. coli, cause UTIs. England recorded 189,756 UTI-related hospital admissions in the financial year 2023 to 2024, with 1.2 million NHS bed-days, according to the government's 2025 report.[2] Those figures show why clinicians must treat genuine infection while avoiding antibiotics when they aren't needed.
For a clear lower UTI, antibiotics can shorten symptoms and reduce the risk of infection moving upwards towards the kidneys. They aren't a casual add-on, but neither should you use leftover tablets or buy medicines from an unregulated website.
A urine dipstick may help in some adults, but it doesn't suit every situation. Symptoms, age, sex, pregnancy, medical history and previous culture results all affect the decision.
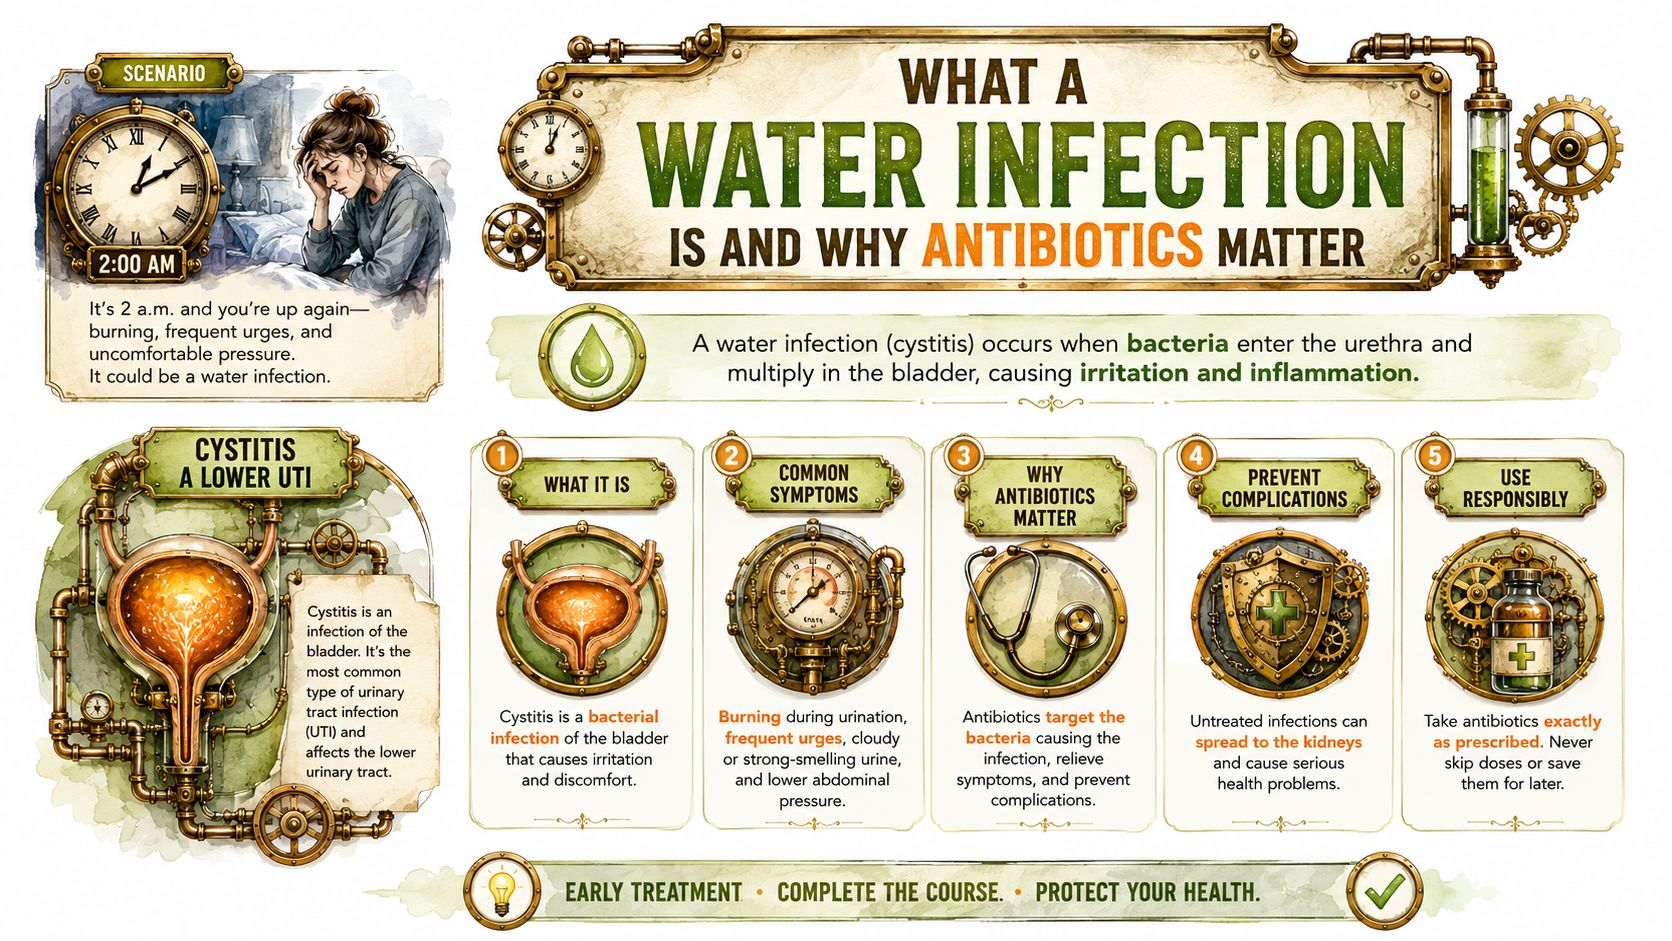
Five practical points to remember
- Recognise the pattern: Burning, urgency and frequency often fit cystitis, but vaginal symptoms or unusual pain may suggest another cause.
- Drink normally: Hydration supports comfort, but forcing large volumes won't reliably clear an infection.
- Expect a different pathway: Men, pregnant women and children under 16 need prompt clinical assessment rather than casual self-treatment.
- Use testing wisely: A dipstick or urine culture may help when the diagnosis isn't clear or treatment fails.
- Act on warning signs: Fever, flank pain, vomiting, confusion or blood in the urine make self-care unsafe.
For a plain-language overview of bladder symptoms, see this guide to cystitis symptoms and treatment. Don't delay medical advice if symptoms are severe, unusual or getting worse.
NHS first-line antibiotics for water infection explained
For non-pregnant women with classic lower UTI symptoms, a pharmacist or GP may diagnose cystitis from the symptom pattern. A urine culture often isn't needed at the first visit. Men, pregnant women, people with recurrent infections and those who recently used antibiotics may need a sample sent to a laboratory before or alongside treatment.
NICE recommends different medicines according to kidney function and resistance risk. For a non-pregnant adult with uncomplicated cystitis, the recommendation is nitrofurantoin 100 mg modified-release twice daily for 3 days when eGFR is 45 ml/minute or more.[3] eGFR estimates how well the kidneys filter blood.
How the main options fit
- Nitrofurantoin: Usually the preferred first option when kidney function allows. It concentrates in urine, which makes it useful for bladder infection, but it isn't suitable for suspected kidney infection.
- Trimethoprim: NICE supports 200 mg twice daily for 3 days when the risk of resistance is low.[3] It may not work if local resistance is high or a previous culture showed resistance.
- Pivmecillinam: This can provide an alternative where nitrofurantoin isn't suitable or resistance makes another option preferable. NICE lists 400 mg three times daily for 3 days for suitable adults.[3]
- Fosfomycin: A 3 g single dose may have a role in selected cases, usually after a clinician considers the infection history and likely susceptibility.
NICE gives different course lengths for some groups. For example, treatment may last longer in men or pregnant women, so don't assume a short course applies to everyone.
Pharmacist's tip: Tell the prescriber about your latest eGFR, recent antibiotics, allergies and any previous urine culture. These details can change the safest first choice.
A practical nitrofurantoin MR 100 mg capsule assessment should still include safety questions. An online form or pharmacy consultation shouldn't just ask whether you have cystitis, then issue tablets without checking for kidney symptoms.
When pharmacy treatment isn't enough
Seek urgent NHS advice instead of relying on self-care if you have fever, shaking chills, pain in your side or back, vomiting, marked weakness, confusion or visible blood. Pregnancy, male sex, childhood symptoms and suspected kidney involvement also need a clinical route rather than routine self-treatment.
Comparing nitrofurantoin trimethoprim and pivmecillinam
The simplest comparison is not “which antibiotic is strongest?” A better question is, which medicine is most likely to treat this bladder infection safely and narrowly?
| Feature | Nitrofurantoin | Trimethoprim | Pivmecillinam |
|---|---|---|---|
| Drug group | Urinary antibiotic | Antibiotic that blocks bacterial folate use | Penicillin-related antibiotic |
| Typical adult lower UTI dose | 100 mg modified-release twice daily | 200 mg twice daily | 400 mg three times daily |
| Typical uncomplicated course | 3 days for suitable non-pregnant adults | 3 days for suitable non-pregnant adults | 3 days for suitable adults |
| Kidney function | Use when eGFR is 45 ml/minute or more | Dose and suitability need clinical review | Avoid below eGFR 10 ml/minute |
| Resistance picture | Low in UK surveillance | Higher and locally variable | Generally low in available UK data |
| Common side effects | Nausea, stomach upset, headache | Nausea, rash and stomach upset | Nausea, diarrhoea and rash |
| Pregnancy and breastfeeding | Needs clinician review | Avoid in the first trimester unless a specialist advises otherwise | Needs clinician review |
| Interactions and cautions | Kidney disease and certain lung or liver problems matter | Methotrexate, some blood-pressure medicines and kidney problems may matter | Penicillin allergy and kidney function matter |
| Food and timing | Taking it with food can improve absorption and reduce stomach upset | Follow the label and keep doses evenly spaced | Follow the label and complete the prescribed course |
| NHS cost | Depends on the prescription and supply | Depends on the prescription and supply | Depends on the prescription and supply |
| Pharmacy First or online use | May be available after assessment | May be available after assessment | Often requires a GP or another prescriber, depending on service access |
The exact choice depends on your history, examination and local policy. NICE's lower UTI guidance supports nitrofurantoin first for suitable non-pregnant adults, with trimethoprim reserved for a low resistance risk.[3]
Reading the table safely
A medicine's side-effect list doesn't tell you whether it fits your infection. Nitrofurantoin may be a poor choice when kidney filtration is reduced, while trimethoprim may be unreliable where resistance is common. Pivmecillinam can be useful, but availability and the prescriber's assessment matter.
A trimethoprim 200 mg tablet consultation should check recent antibiotic use and medicines that can interact. Don't swap one antibiotic for another because a previous course worked. The bacteria, your kidney function and the infection site may have changed.
Why UK resistance patterns shape your first-line choice
Trimethoprim is familiar and can be convenient, but familiarity doesn't guarantee success. UK surveillance has repeatedly shown much higher E. coli resistance to trimethoprim than to nitrofurantoin.
NICE's evidence summary reports national E. coli resistance in laboratory-processed urine specimens at 30.3% for trimethoprim, compared with 2.5% for nitrofurantoin, 7.5% for pivmecillinam and 9.9% for cefalexin.[1] Local figures vary, so a result from your own urine culture can be more useful than a national average.
| Antibiotic | Typical UK resistance finding | Implication for first-line use |
|---|---|---|
| Nitrofurantoin | 2.5% national resistance in the NICE evidence summary | Often a reliable empirical option when eGFR allows |
| Trimethoprim | 30.3% national resistance in the same summary | Use when resistance risk is low |
| Pivmecillinam | 7.5% national resistance in the same summary | Useful alternative when clinically appropriate |
| Cefalexin | 9.9% national resistance in the same summary | Not automatically the narrowest or best first choice |
Earlier UK surveillance found trimethoprim resistance at 34% in community settings and 37% in acute care settings, while nitrofurantoin resistance was 2.7% and 3.2%, respectively.[2] Separate English surveillance found nitrofurantoin non-susceptibility of 0.9% in sentinel data and 1.5% in routine laboratory data, compared with 28.2% and 33.4% for trimethoprim.[4]
The kidney function trade-off
Nitrofurantoin's strong urinary activity doesn't remove its kidney limit. NICE recommends it for uncomplicated lower UTI only when eGFR is at least 45 ml/minute.[3] This threshold matters particularly for some older adults, whose kidney function may have fallen without obvious symptoms.
If nitrofurantoin isn't suitable, a prescriber may consider pivmecillinam or another agent. The decision should reflect the likely site of infection, allergies, previous cultures and local guidance.
Wider access and stewardship
Pharmacy First monitoring found nitrofurantoin resistance remained stable at 2.1% in 2023 and 2.2% in 2024 after supply through the service.[5] That short-term finding doesn't prove that resistance can never rise, but it challenges the assumption that easier access automatically worsens resistance.
Practical rule: Ask whether a urine culture exists, whether local resistance is known and why the selected course length fits your situation.
Safe self-care and when to seek help quickly
Antibiotics address bacteria. They don't instantly remove bladder irritation, so sensible self-care can make the waiting period more bearable.
Use paracetamol for pain if it's safe for you and follow the label. Ibuprofen may help some adults, but avoid it or ask a pharmacist first if you have kidney disease, stomach ulcers, heart failure, are pregnant, take certain medicines or have been told to avoid anti-inflammatory painkillers.
Comfort measures that make sense
- Drink to thirst: Keep fluids steady rather than forcing excessive amounts.
- Reduce irritants: Caffeine and alcohol can make urgency or bladder discomfort feel worse.
- Try gentle warmth: A heat pack over the lower abdomen may ease suprapubic discomfort.
- Take doses correctly: Follow the label, finish the prescribed course and don't share tablets.
- Review the response: Burning, urgency and frequency should start to settle. If they haven't improved by 48 hours, contact a GP or pharmacist for review.
Cystitis sachets and cranberry products may be optional additions for some people, but they don't replace antibiotics when a clinician says antibiotics are needed. D-mannose also shouldn't become a reason to delay assessment.

Recurrent and catheter-related symptoms
Clinicians commonly define recurrent UTI as two or more episodes in six months, or three in twelve months. Repeated symptoms deserve a review of diagnosis, urine cultures, triggers and prevention, rather than an endless cycle of repeat prescriptions.
Catheter-associated UTI follows a different pathway. Bacteria in a catheter urine sample without symptoms, known as asymptomatic bacteriuria, shouldn't normally receive antibiotics. A clinician must interpret the symptoms and the catheter history together.
Same-day help is important for a temperature above 38°C, shaking chills, flank pain, vomiting, confusion in an older adult, blood clots in urine, pregnancy, or symptoms in a man or child. Call NHS 111, contact an urgent treatment service or seek emergency care if you feel seriously unwell.
For recurrent symptoms, ask a clinician whether methenamine hippurate for UTI prevention is appropriate. It isn't a treatment for a suspected kidney infection or a substitute for urgent assessment.
Getting antibiotics online in the UK safely
Legitimate UK online prescribing should look like a clinical consultation, not a shopping basket. A regulated service should identify the prescriber, ask about symptoms and check whether an antibiotic is suitable.
What a proper assessment should cover
Expect questions about:
- Symptoms and timing: Burning, frequency, urgency, pain, fever and how long they've lasted.
- Risk factors: Pregnancy, sex, age, catheter use, kidney disease and recurrent infections.
- Medicines and allergies: Recent antibiotics, regular medicines and previous reactions.
- Previous results: Urine cultures, resistant bacteria and failed treatments.
- Safety signs: Flank pain, vomiting, confusion or symptoms suggesting a kidney infection.
A GPhC-registered pharmacy or clinic may decide on an antibiotic, delayed treatment or self-care advice. Nitrofurantoin and trimethoprim may be supplied through an online route where the service's clinical rules allow it. Pivmecillinam may require a GP because availability differs.
Online prescribing isn't the right route for everyone. Men, children, pregnant patients, people with recurrent infections, anyone with red flags and anyone with suspected kidney involvement should seek direct NHS assessment or another appropriate clinical service.

Checks before you pay
Look for a UK address, a visible GPhC registration number, the prescriber's identity and a clear complaints process. The service should explain what happens if symptoms don't improve and how it handles follow-up.
A urine culture generally isn't needed for uncomplicated cystitis in a non-pregnant woman, but it becomes more important when symptoms are atypical, recurrent or persistent. You can read about the UK online pharmacy assessment process before choosing a service.
Summary FAQs and what to do next
For suitable non-pregnant adults with uncomplicated cystitis, nitrofurantoin usually leads when kidney function allows. Trimethoprim fits only when resistance risk is low, while pivmecillinam can provide an alternative after clinical review. Take prescribed doses as directed, use simple pain relief if safe and don't ignore worsening symptoms. Fever, flank pain, vomiting, confusion, pregnancy, childhood symptoms and male symptoms need prompt NHS advice. Recurrent infections call for a planned review and often a urine culture.
How quickly should antibiotics improve cystitis symptoms?
Many people start to feel better after treatment begins, but irritation can take time to settle. If symptoms haven't started improving within 48 hours, contact a GP or pharmacist rather than waiting indefinitely.
Can a pharmacist prescribe antibiotics through Pharmacy First?
A pharmacist may assess eligible people and supply treatment through Pharmacy First when the service rules allow it. The pharmacist should still check symptoms, risk factors, medicines and warning signs.
Is nitrofurantoin always the best antibiotic?
No. It often suits uncomplicated lower UTI when eGFR is at least 45 ml/minute, but kidney function, pregnancy, allergies, suspected kidney infection and resistance can change the choice.[3]
Can cranberry juice replace antibiotics?
No. Cranberry products may be an optional adjunct for some people, but they don't replace antibiotics when a clinician diagnoses an infection that needs treatment.
Does D-mannose cure a water infection?
Don't rely on D-mannose to treat an active UTI. Persistent or worsening symptoms need assessment, especially if you have fever, flank pain or vomiting.
When should I request a urine culture?
Ask about a culture when infections keep returning, symptoms are unusual, treatment fails or you recently used antibiotics. Men, pregnant women and children may need testing as part of their initial assessment.
What should I do today?
Call your GP surgery or use NHS Pharmacy First if your symptoms fit uncomplicated cystitis and you have no warning signs. Seek same-day help through NHS 111 or an urgent treatment service if you have red flags. If you're choosing an online route, use only a regulated UK service with a clinician-led assessment.
This information is for general education and isn't a substitute for medical advice, diagnosis or treatment.
If you need a regulated online assessment for possible uncomplicated cystitis, Courier Pharmacy offers clinician-reviewed questionnaires for suitable prescription requests. Use the service only if you have no red-flag symptoms, and seek NHS care promptly when your symptoms need an examination or urine culture.
Suggested internal links
- Cystitis symptoms and treatment
- Nitrofurantoin MR 100 mg capsules
- Trimethoprim 200 mg tablets
- Methenamine hippurate for UTI prevention
- Online pharmacy services in the UK
Visual suggestions
- Symptom pathway infographic: Bright lime green bladder diagram, pale yellow-green symptom panels and ornate brass plaque labels. Alt text: “Illustrated pathway showing bladder infection symptoms and warning signs.”
- Antibiotic comparison chart: Painterly steampunk medicine bottles in light grey, with brass plaques for kidney function and resistance checks. Alt text: “Comparison of UK antibiotics used for uncomplicated cystitis.”
- Safety checklist: Lime checkmarks beside hydration, pain relief, medicine timing and urgent warning signs. Alt text: “Checklist for safe self-care during a bladder infection.”
- Online prescribing flow: Four brass plaque stages showing assessment, clinician review, prescription and regulated dispensing. Alt text: “Four-step UK online pharmacy assessment process for cystitis treatment.”
Meta description
Antibiotics for water infection UK explained, including first-line choices, kidney function, resistance, self-care, Pharmacy First and urgent warning signs.
Byline and clinical review
Written by: Medical Mojo editorial team, health information writers.
Clinically reviewed by: UK-registered pharmacist, credentials to be confirmed before publication.
How this content was created
This article uses NICE lower UTI guidance, UK government surveillance, peer-reviewed English resistance data and Pharmacy First monitoring. The content was checked against the supplied prescribing information and written for UK adults in plain English.
References
[1] National Institute for Health and Care Excellence (NICE) (2018) Urinary tract infection, lower, antimicrobial prescribing, NG109. Available at: NICE guideline NG109
[2] UK Government (2025) Antibiotic-resistant infections continue to rise. Available at: UK Government antibiotic resistance report
[3] National Institute for Health and Care Excellence (NICE) (2018) Recommendations, urinary tract infection, lower, antimicrobial prescribing. Available at: NICE prescribing recommendations
[4] Bou-Antoun, S. et al. (2021) ‘Antimicrobial resistance in urinary tract infections in England', Journal of Antimicrobial Chemotherapy. Available at: Peer-reviewed urinary resistance analysis
[5] Drazich-Taylor, M. et al. (2025) ‘Pharmacy First and antimicrobial resistance monitoring', Journal of Antimicrobial Chemotherapy, Antimicrobial Resistance. Available at: Pharmacy First resistance monitoring


