MRSA Treatment Regimen UK: A Clear Patient Guide
Get a clear guide to the MRSA treatment regimen UK. Learn about decolonisation, treating skin infections, hospital care, and NHS guidance for 2026.

SEO brief
- Primary keyword: MRSA treatment regimen UK
- Secondary keywords: MRSA decolonisation UK, MRSA carrier treatment, MRSA skin infection treatment UK, hospital MRSA treatment, MRSA antibiotics UK
- Search intent: Informational. Reader wants a clear, practical explanation of what treatment they may get in the UK and what to do next.
- Target reader: UK adults, carers, and family members after an MRSA swab, diagnosis, or hospital discussion
- Product/service mention: Online pharmacy support where clinically appropriate
- Internal links available: Assumed from brief and included where requested
MRSA treatment in the UK depends entirely on whether you are a carrier or have an active infection. If you're a carrier, treatment is usually a 5-day decolonisation course with a special body wash and nasal cream. If you have an active infection, you may need specific antibiotics, and the type and length depend on how serious the infection is.
If you've just been told you have MRSA, it's easy to jump to worst-case thoughts. Often, the first point of clarification is: are you carrying the bacteria on your skin or in your nose, or is it causing an infection? That difference decides everything that comes next.
You'll learn what MRSA means, why you may have been tested, what a UK decolonisation routine usually involves, when antibiotics are used, and what to do if MRSA seems to come back.
What is MRSA and why was I tested
MRSA stands for meticillin-resistant Staphylococcus aureus. That sounds alarming, but the basic idea is simple. It's a common type of bacteria that has become resistant to some antibiotics.
Many people carry Staphylococcus aureus on their skin or in their nose without feeling unwell. If it's MRSA, the same can happen. In that situation, the bacteria are present, but they are not causing harm.

You were probably tested for one of two reasons:
- Routine screening before hospital care. This often happens before an operation or admission.
- Symptoms of infection. For example, a boil, infected wound, painful redness, or a fever with a suspected bacterial infection.
Carrier versus infection
At this point, readers often get mixed up.
A carrier has MRSA living on the body, often in the nose, without signs of illness. An active infection means the bacteria are causing a problem, such as a skin infection, wound infection, pneumonia, or bloodstream infection.
Practical rule: If your treatment sounds like a nasal cream and body wash, your team is usually treating carriage. If they talk about tablets, drips, scans, blood tests, or a longer course, they are treating an infection.
In UK practice, community-associated MRSA is now very uncommon, so doctors usually do not treat common skin infections as MRSA unless tests confirm it or there is a strong clinical reason to suspect it [3]. That helps avoid unnecessary antibiotics.
Why the hospital bothers screening
Hospitals screen because carrying MRSA can matter before surgery or if you're very unwell. Reducing the bacteria on the body can lower the chance of spread and help protect wounds and lines. UK intensive care data also showed major improvements alongside prevention and decolonisation measures, with MRSA bloodstream infections falling by 97%, from 25 to 4 new cases per 1,000 patients, between 2007 and 2016 [2].
The two paths of MRSA treatment decolonisation vs active infection
The phrase MRSA treatment regimen UK can be misleading because it sounds like there's one standard plan for everyone. There isn't. There are two very different paths.
Think of it as prevention versus treatment
Decolonisation is for someone carrying MRSA. It is comparable to clearing weeds before they spread. The aim is to reduce the amount of bacteria on the body.
Active infection treatment is different. That's for when the bacteria are already causing illness. Then the aim is to treat the infected area properly and prevent complications.
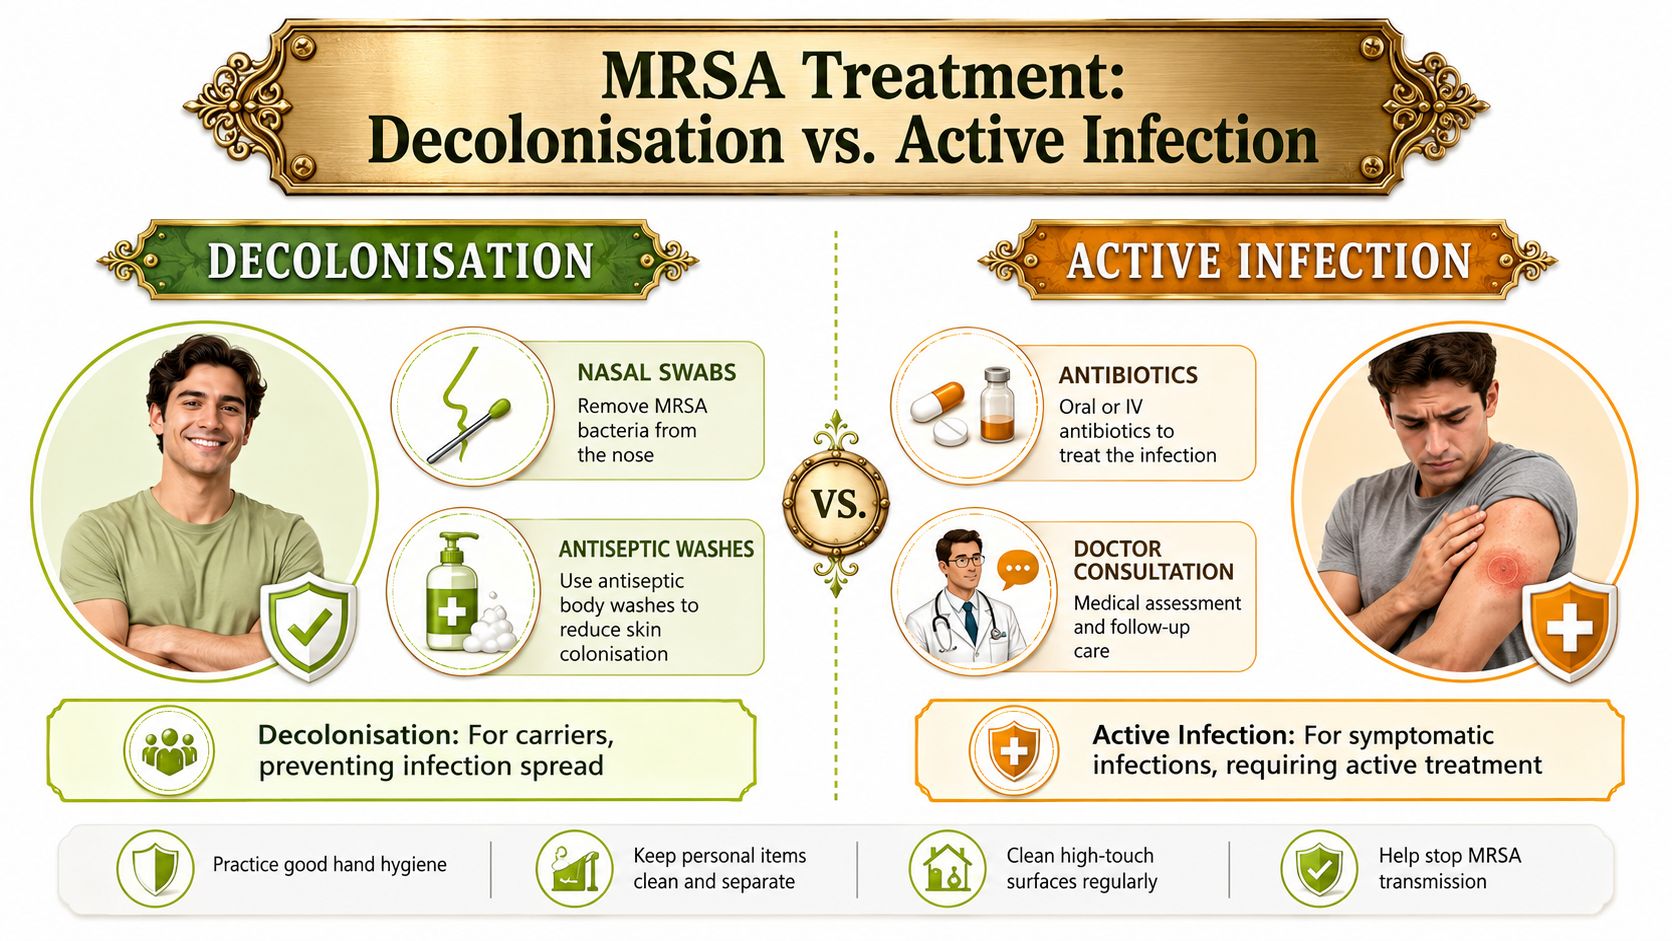
UK guidance separates these pathways clearly. Topical decolonisation for carriers usually involves a 5-day course of mupirocin nasal cream and a chlorhexidine body wash, while invasive infections may need intravenous drugs such as vancomycin or teicoplanin, sometimes for much longer [4].
MRSA carrier vs active infection at a glance
| Aspect | MRSA Carrier (Decolonisation) | Active MRSA Infection (Treatment) |
|---|---|---|
| What it means | Bacteria present but not causing illness | Bacteria are causing symptoms or disease |
| Main aim | Lower bacterial load and reduce spread | Treat the infection itself |
| Typical treatment | Nasal mupirocin and chlorhexidine wash | Drainage, oral antibiotics, or IV antibiotics depending on site |
| Usual setting | Home, often around surgery or screening | GP, urgent care, or hospital |
| Typical duration | Often 5 days [4] | Depends on severity and infection type [1] |
| What confuses people | “Why do I need treatment if I feel fine?” | “Why is my treatment so much longer?” |
A short nasal-and-wash course is not a “milder version” of hospital antibiotic treatment. It's a different pathway for a different problem.
Your UK decolonisation regimen a practical guide
If your swab shows you're an MRSA carrier, your team may ask you to do a short decolonisation routine at home. This is common before planned surgery.
What the standard routine usually includes
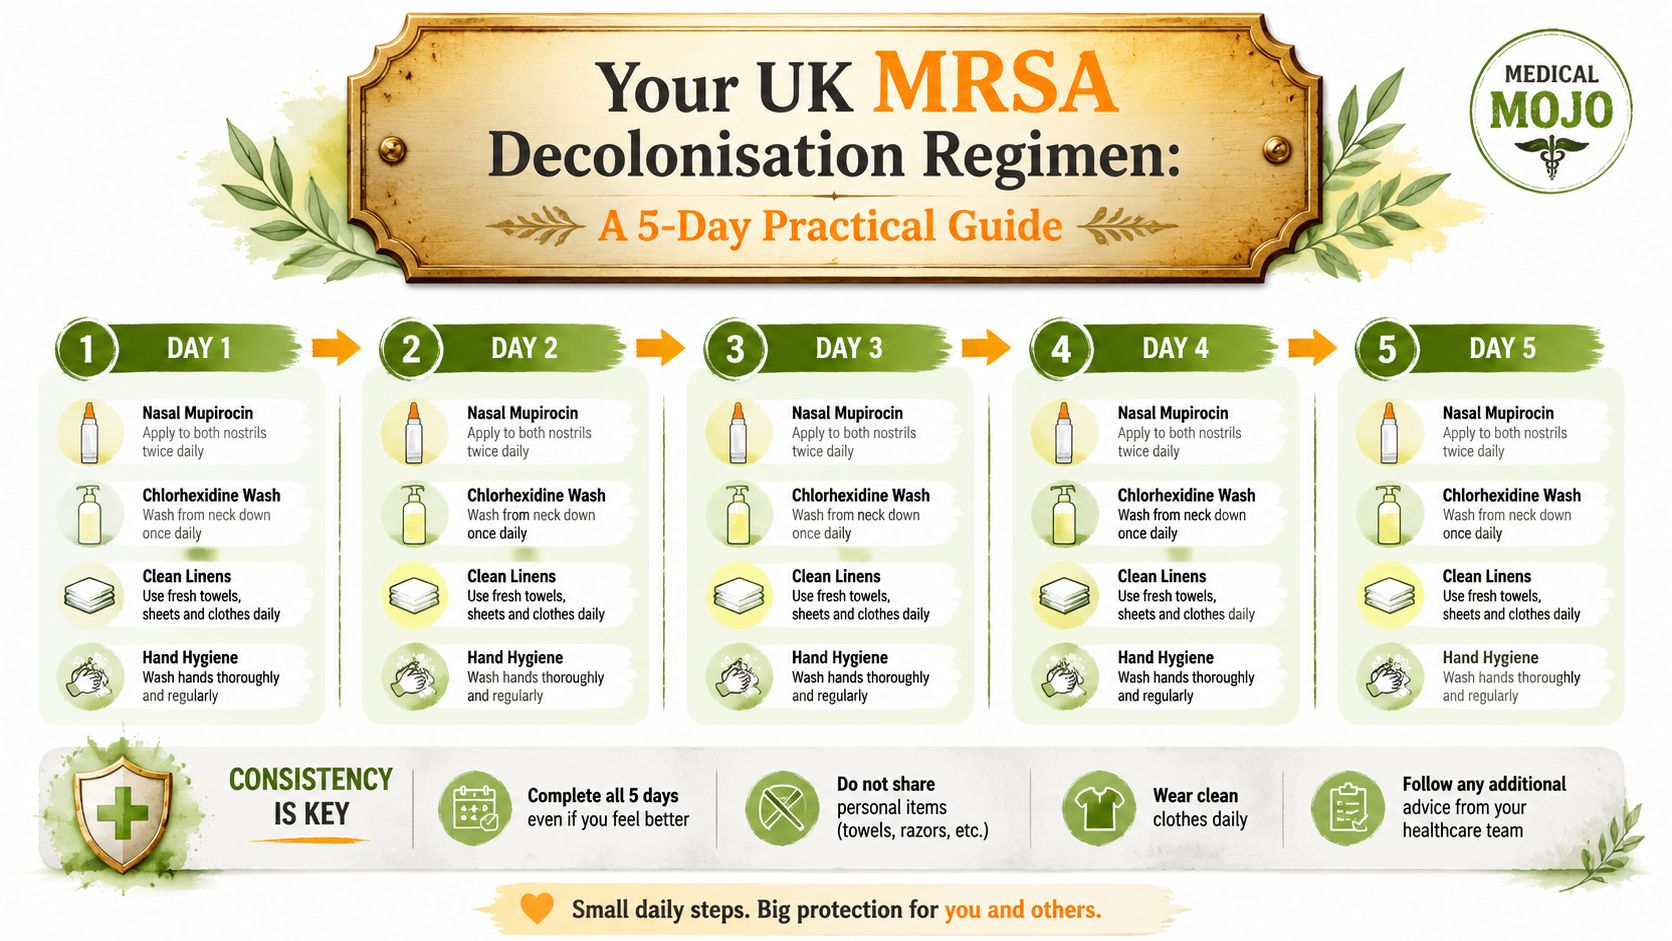
The standard UK approach uses nasal mupirocin with a chlorhexidine body wash. NHS guidance says people found to have MRSA on screening are usually treated for around 5 to 10 days with a nasal cream or spray plus body wash and shampoo [2].
People often ask if this means they're “infected”. Usually, no. It means the team wants to reduce MRSA on your body before it has a chance to cause trouble.
A simple day by day routine
A practical routine often looks like this:
- Use the nasal treatment as instructed. This is usually mupirocin in the nostrils.
- Wash with the antiseptic product daily. Follow the label or hospital instructions carefully.
- Use fresh towels and clean clothes. This helps reduce re-spread on the skin.
- Change bed linen during the course if advised.
- Wash hands well after touching your nose, dressings, or skin lesions.
Here's the video guide included in the brief for readers who prefer a visual walk-through:
Fitting it into real life
A busy parent waiting for a hip replacement might do the body wash in the shower each evening, then apply the nasal cream before bed and again at another set time each day. Keeping the products beside your toothbrush or medicines box can help you remember.
A shift worker might tie the routine to waking up rather than to morning or night. The key is consistency.
Pharmacist's tip: Apply nasal cream after gently blowing your nose. That helps the medicine reach the inside lining better.
Pharmacist's tip: Chlorhexidine can irritate some skin. If your skin becomes sore, ask your GP, hospital team, or pharmacist before stopping.
Pharmacist's tip: If you forget a dose, take it when you remember unless it's nearly time for the next one. Don't double up.
If you're prescribed a specific nasal product, use the one your clinician recommends. Some patients also look up common nasal treatment options such as Naseptin nasal cream, but don't swap products without checking first because the planned regimen may be very specific.
Treating active MRSA skin and soft tissue infections
This is the part many people expect to be simple. Boil equals antibiotic. In real life, it's often not that straightforward.
When a boil needs draining not just tablets
For abscesses, incision and drainage is essential in UK guidance [3]. That means a clinician may need to open and drain the trapped pus. Antibiotics alone often don't do the whole job if the collection stays sealed off.
A realistic example is a parent whose child keeps getting painful boils. The family may assume stronger tablets are the answer. But if the boil forms an abscess, the main treatment may be drainage first, then careful wound care.
Don't squeeze or lance an abscess at home. That can worsen the infection and spread bacteria.
If you want general background on common skin infections, this overview of skin infections can help with plain-language context. It's not a substitute for a clinician looking at a possible abscess.
When antibiotics may be added
UK guidance says systemic antibiotics are added for larger lesions, surrounding cellulitis, multiple-site infection, or if the patient is unwell or not improving after drainage [3].
The oral options may include:
- Co-trimoxazole
- Doxycycline
- Clindamycin
But there's an important catch. These are used only when the lab shows the MRSA is susceptible. Doctors try to avoid unnecessary anti-MRSA antibiotics because overuse adds selective pressure and can drive resistance [3].
Featured answer:
Do all MRSA skin infections need antibiotics?
No. In the UK, abscesses often need drainage first, and antibiotics are added only in some situations [3].
Hospital treatment for serious MRSA infections
When MRSA causes a bloodstream infection, pneumonia, or bone infection, the treatment changes completely. This is why families sometimes feel shocked by drips, scans, long courses, and specialist reviews.
Why hospital treatment is more intensive
For severe MRSA infections, UK guidance uses longer treatment based on the site and severity of infection. Evidence summaries note that UK recommendations were updated over time as resistance patterns changed and newer agents became available. They include at least 14 days of antibiotics for uncomplicated MRSA bacteraemia and at least 28 days for complicated bacteraemia [1].
Bone and joint infection may need 4 to 6 weeks total therapy [4]. Hospital teams often use intravenous drugs such as vancomycin or teicoplanin, and later UK commentary notes wider use of linezolid and daptomycin after 2008 [1].
What families often notice on the ward
You may notice frequent blood tests, drug level checks, heart scans, or changes in antibiotics. That doesn't automatically mean treatment is failing. It often means the team is making sure the antibiotic is working safely and that they've found the infection source.
A relative may also hear the term “bacteraemia”. That means bacteria in the bloodstream. If you're trying to make sense of repeated blood tests, this plain-language guide to the full blood count test can help you understand one part of the monitoring.
“Longer treatment for a serious MRSA infection is standard care, not a sign that your body is unusually weak.”
Featured answer:
Why am I on IV antibiotics for so long?
Because serious MRSA infections need high drug levels and longer courses. Bloodstream and bone infections are treated very differently from simple skin carriage [1][4].
Self-care at home and what to do if MRSA returns
Once you're home, the aim is simple. Help your body recover, lower the risk of spread, and know what changes need a call for help.
Practical steps at home
Focus on the basics:
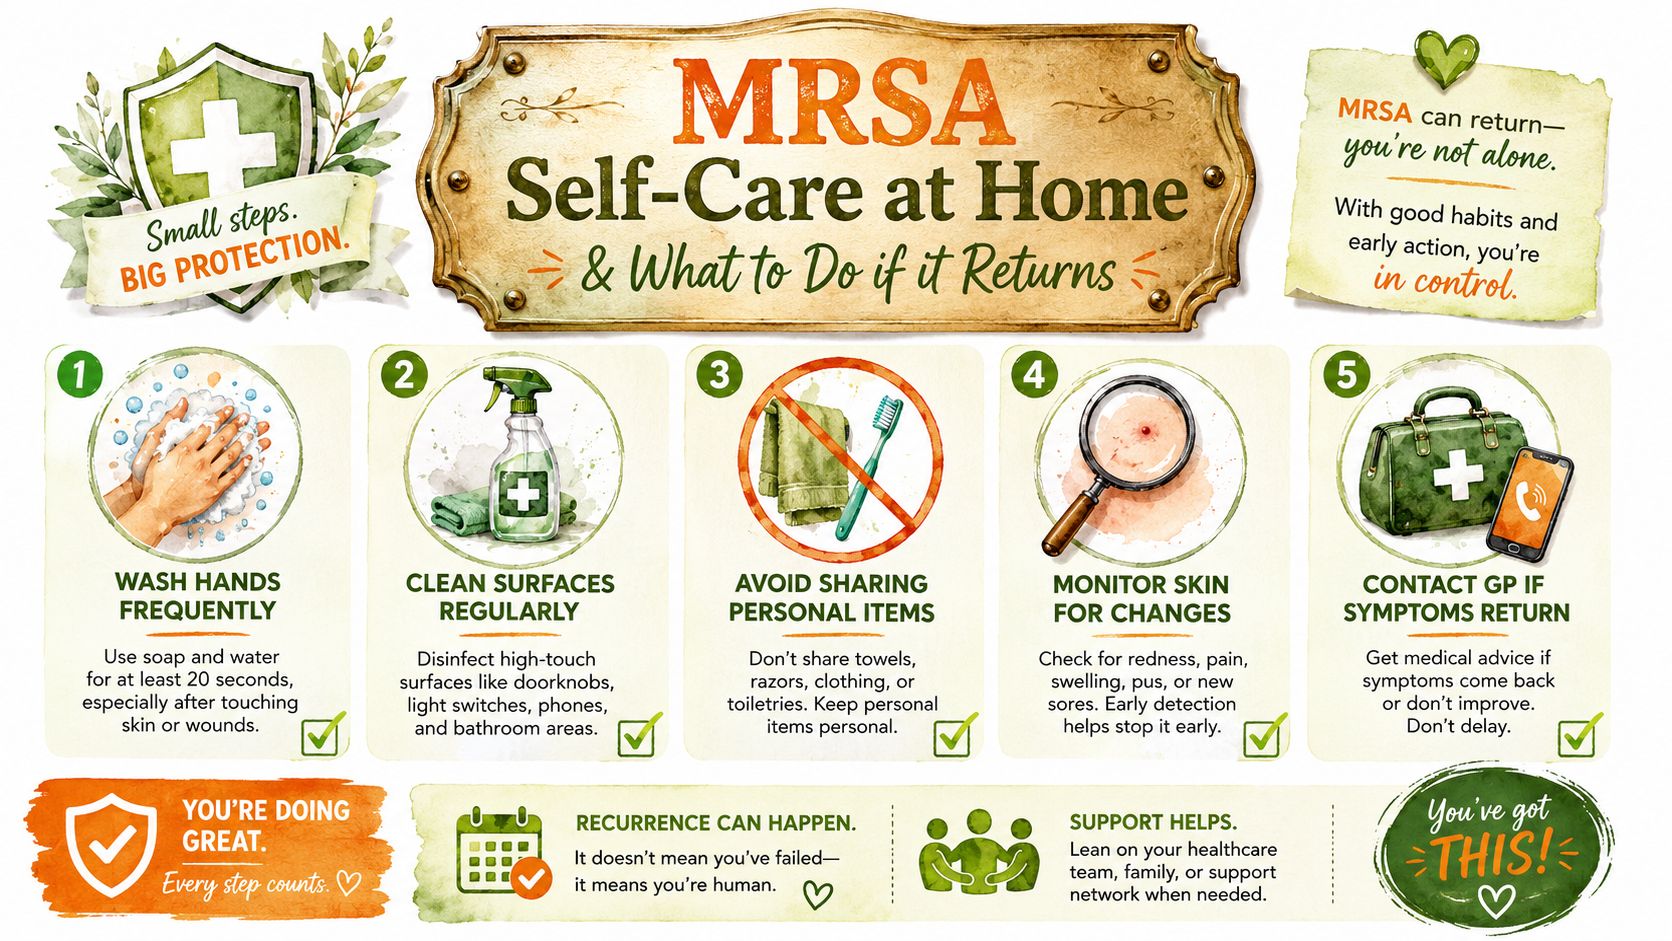
- Wash your hands well. Especially after touching dressings, wounds, or your nose.
- Keep wounds covered. Clean, dry dressings help protect others and the healing skin.
- Don't share personal items. Towels, razors, face cloths, and clothing can pass bacteria around.
- Clean touched surfaces. Bathrooms and shared items need regular cleaning.
- Finish treatment as prescribed. Stopping early can make things harder to manage.
A gym-goer with a healing skin infection might need to pause contact sports, keep the area covered, and avoid sharing towels. A care worker might need occupational advice about dressings and return to work.
Why MRSA can seem to come back
This question upsets people more than almost any other.
UK infection control guidance says decolonisation does not usually eradicate MRSA permanently. It often suppresses carriage rather than removing it forever, and repeated use of mupirocin and chlorhexidine can drive resistance, which is why monitoring matters [5]. The same guidance also notes there is generally no need for routine repeat screening after treatment [5].
That can feel counterintuitive. Many people think more swabs must always be better. In practice, your clinical team decides whether another swab is useful based on your situation.
If you're browsing common skin treatments online, remember that products such as those discussed in this guide to Fucidin cream for skin infections are not a stand-in for an MRSA-specific plan. The right treatment depends on the organism and its susceptibilities.
When to get urgent medical help
Seek urgent medical advice if you have:
- Spreading redness
- Severe pain or swelling
- A high fever or shaking chills
- Shortness of breath
- Confusion
- A wound that suddenly looks much worse
Featured answer:
If MRSA comes back, does that mean the first treatment failed?
Not necessarily. Decolonisation often reduces MRSA for a time rather than removing it forever [5].
Frequently asked questions about your MRSA treatment
Can I be around my family if I have MRSA?
Usually, yes. Good hand hygiene, covered wounds, and not sharing towels or razors matter most. If someone at home is very vulnerable, ask your clinician for specific advice.
Do I need to deep clean the whole house?
Usually not in an extreme way. Normal regular cleaning, laundry, and sensible hygiene are the main steps. Focus on commonly touched surfaces and personal items.
Can I go to work with MRSA?
Often yes, depending on the job and whether you have an active draining wound. Healthcare, care work, and food handling may need extra advice. Ask your employer's occupational health team if needed.
Why didn't my doctor give me antibiotics straight away?
Because not every suspected MRSA problem needs them. For abscesses, drainage may matter more than tablets, and doctors try to avoid unnecessary anti-MRSA antibiotics [3].
Is a carrier the same as having an infection?
No. A carrier has the bacteria present without illness. An infection means the bacteria are causing symptoms and need active treatment.
Do I need repeat swabs after decolonisation?
Not routinely in every case. UK infection control guidance says routine repeat screening is generally not needed [5]. Your team may still advise follow-up in specific situations.
What should I tell a future hospital team?
Tell them you've had MRSA before, whether it was carriage or infection, and what treatment you had. That helps them plan screening or precautions.
Can an online pharmacy help with treatment?
An online pharmacy may help with advice, prescribed treatments where appropriate, and medicine supply under UK regulation. If you need general pharmacy support, Courier Pharmacy's online pharmacy service is one example of a regulated route for medicines and advice. For serious symptoms, use urgent NHS services instead.
Will I always have MRSA now?
Not necessarily. Some people clear it, some carry it for a time, and some have it return. The main thing is to follow the plan you're given and get reviewed if symptoms come back.
Is MRSA always dangerous?
No. It can be harmless carriage, a treatable skin infection, or a serious infection depending on where it is and how unwell the person is. The key is matching the treatment to the situation.
If you need help understanding a prescription, getting practical advice about medicines, or arranging treatment through a regulated UK service, Courier Pharmacy is one option to explore. Always use your GP, NHS 111, or urgent care if you have spreading infection, fever, breathing problems, or any signs of serious illness.
Summary
MRSA isn't one single problem, so there isn't one single treatment plan.
In the UK, the first question is whether you're a carrier or whether you have an active infection.
Carriers usually get a short course of nasal treatment and antiseptic body wash.
Skin infections may need drainage, and antibiotics are used more carefully than many people expect.
Serious infections in hospital need longer treatment and closer monitoring.
If MRSA returns, that doesn't always mean anyone got it wrong.
Follow your plan, use good hygiene, and ask for review if symptoms worsen.
Meta description:
MRSA treatment regimen UK explained clearly. Learn the difference between carrier treatment and active infection care, plus what to do if MRSA returns.
Suggested internal links for medicalmojo.co.uk
- A patient guide to skin infections and when to seek help
- How antibiotics are chosen and why resistance matters
- Understanding hospital screening tests before surgery
- What blood culture tests and full blood counts can show
- Wound care basics for healing at home
Byline
Written by Medical Mojo Editorial Team, patient education writers
Clinical review
Clinically reviewed by a UK-registered pharmacist
How this content was created
This article was written using UK guidance and peer-reviewed evidence listed below, then shaped into plain English for patients and carers. A clinical reviewer checked the medical wording, safety points, and consistency with UK practice.
Disclaimer
This information is for general education only and isn't a substitute for personal medical advice. Follow the advice from your GP, hospital team, or pharmacist.
References
[1] Dryden, M., Cooke, J., Salib, R.J., Holding, R. and Biggs, T.C. (2021) ‘Treatment of methicillin-resistant Staphylococcus aureus (MRSA): updated guidelines from the UK', JAC-Antimicrobial Resistance, 3(1), dlaa114. Available at: https://academic.oup.com/jacamr/article/3/1/dlaa114/6127118
[2] National Institute for Health and Care Research (NIHR) (n.d.) ‘Infection control campaigns reduced superbugs in UK ICUs'. Available at: https://evidence.nihr.ac.uk/alert/infection-control-campaigns-reduced-superbugs-in-uk-icus/
[3] Guidelines for UK practice for the diagnosis and management of MRSA infection (PDF). Available at: http://www.jvsmedicscorner.com/ICU-Guidelines_and_Care_Bundles_files/Guidelines%20for%20UK%20practice%20for%20the%20diagnosis%20and%20management%20of%20MRSA%20infection.pdf
[4] Wrightington, Wigan and Leigh Teaching Hospitals NHS Foundation Trust (2025) ‘Methicillin Resistant Staphylococcus Aureus (MRSA) Treatment SOP 3'. Available at: https://www.wwl.nhs.uk/media/FOI/202425/March%202025/10561%20-%20Methicillin%20Resistant%20Staphylococcus%20Aureus%20(MRSA)%20Treatment%20TW10-116%20SOP%203.pdf%20Treatment%20TW10-116%20SOP%203.pdf)
[5] Healthcare Infection Society (n.d.) ‘MRSA guidelines'. Available at: https://www.his.org.uk/guidelines/guidelines-and-guidance-by-topic/mrsa-guidelines/


