Naltrexone for Alcohol Use Disorder: A UK Guide
Naltrexone for alcohol use disorder explained for UK patients — how it works, evidence, dosing, side effects, and how to access treatment online.

SEO brief
Primary keyword: naltrexone for alcohol use disorder
Secondary keywords: oral naltrexone, low-dose naltrexone, alcohol relapse prevention, alcohol craving treatment, UK pharmacy, Sinclair Method
Search intent: Learn what naltrexone does, how it works, how effective it is, and how to access it safely in the UK
Target reader: UK adults, carers, and patients weighing up treatment for alcohol problems
Product/service mention (if any): Courier Pharmacy's regulated online consultation and monitoring pathway
Internal links available: courierpharmacy.co.uk articles on the Sinclair Method, low-dose naltrexone, safety, and blocking endorphin-driven reward
A lot of people reach the point where they've had enough of stop-start drinking, but daily group meetings or a full detox plan still feel out of reach. If that sounds familiar, naltrexone for alcohol use disorder may be one option worth understanding. It's a medicine used to lower the pull to drink, especially when the goal is relapse prevention or cutting down safely, and it works best with follow-up and support rather than as a stand-alone fix. This guide walks through how it works, what the evidence really shows, what side effects matter, and how people in the UK can access it in a practical, regulated way.
What Naltrexone Does for Alcohol Use Disorder
A busy parent in Birmingham may know they're drinking too much, but they can't fit a long clinic timetable around school runs and work. A shift worker in Leeds may want fewer heavy nights, not a lecture about willpower. Naltrexone for alcohol use disorder is one of the medicines that can help with that kind of goal, because it aims to make drinking less rewarding and relapse less likely.
At its simplest, naltrexone is a medicine that helps reduce the urge to keep drinking once you've started. It doesn't “cure” alcohol dependence, and it doesn't replace support, but it can form a useful part of a harm-reduction plan. The strongest evidence supports oral naltrexone 50 mg/day as one of the better-studied options for reducing return to drinking and heavy drinking [1].
You'll often hear people ask whether it works for everyone. The honest answer is no, and that matters. Some people respond well, some don't, and the benefit is usually clearer when there's a structured plan, follow-up, and a clear goal such as fewer drinking days or less heavy drinking [2].
Practical rule: naltrexone works best when the aim is to lower relapse risk, not to act as a quick fix.
What you'll learn here is the part most articles miss. You'll see how naltrexone works, what the trial data really says, how standard and low-dose regimens differ, what side effects to watch for, and how people in the UK can get it through routine care or a regulated online pharmacy route.
Five key takeaways
- Naltrexone can help reduce relapse risk, especially when the plan is clear and realistic.
- The medicine works best with support, not as a stand-alone cure.
- The standard oral dose is 50 mg/day, while low-dose use is a different, off-label approach.
- Opioid medicines and naltrexone don't mix safely, so medication checks matter.
- UK access is possible through NHS or private prescribing, with monitoring built in.
Courier Pharmacy's Sinclair Method guide is a useful next read if you want the behaviour and medication side of this approach explained in plain English.
How Naltrexone Works in the Brain
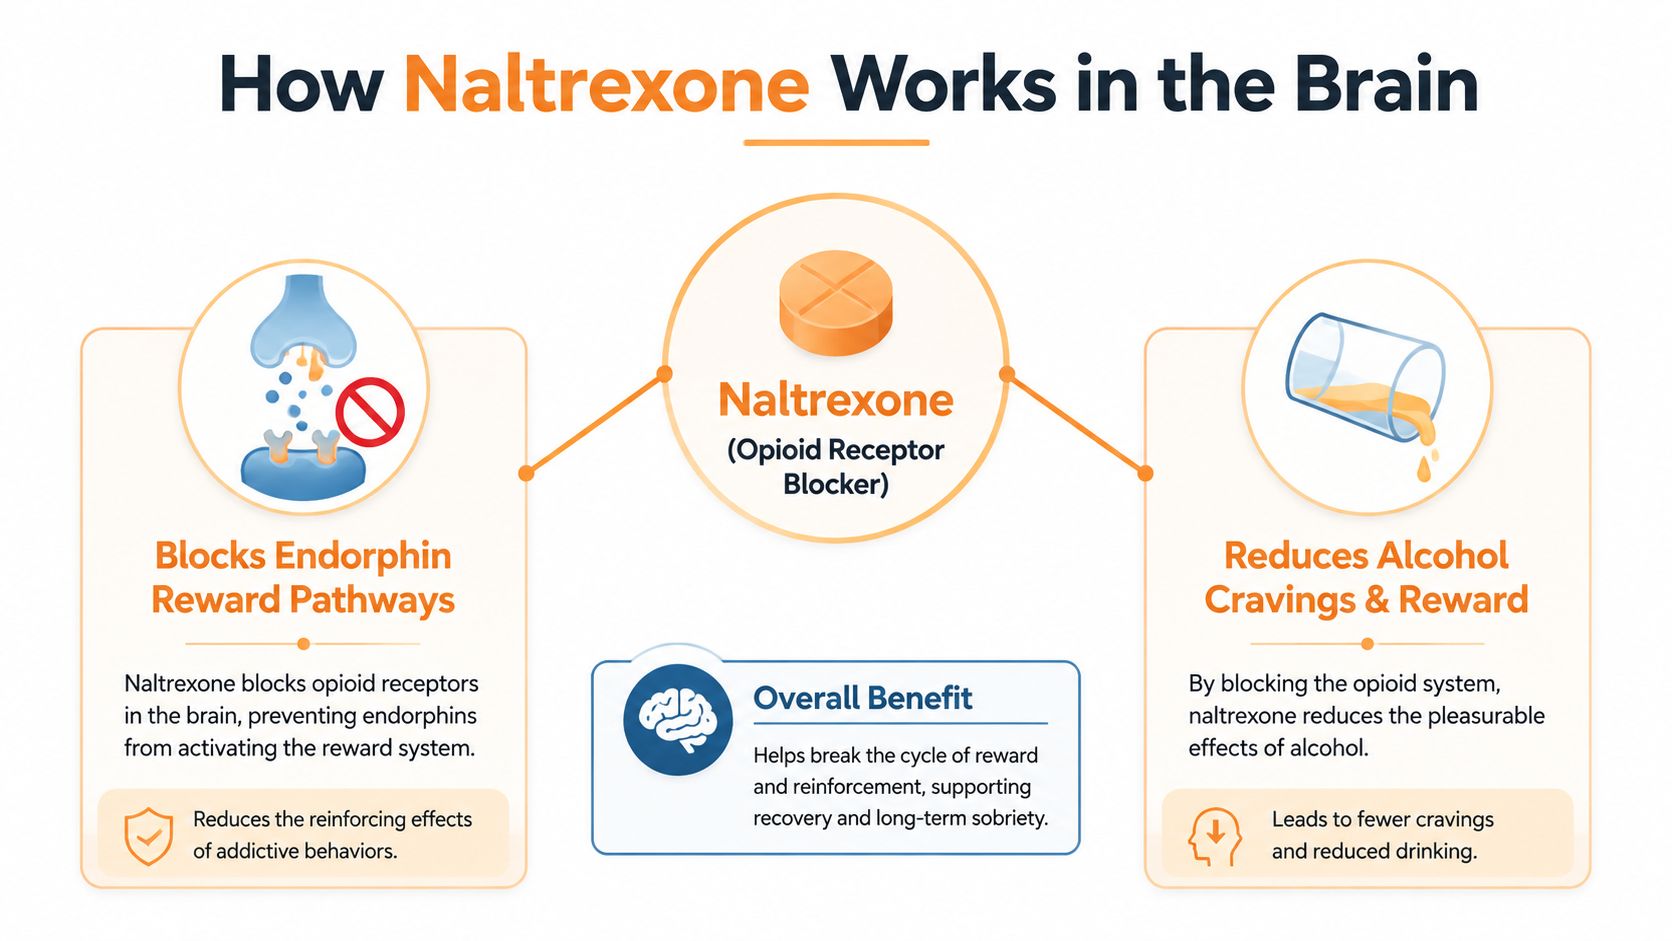
Naltrexone is an opioid receptor blocker. In plain English, it sits on the same brain receptors that natural endorphins use, and it makes the “reward” from alcohol feel smaller. That's why people often describe it as turning down the pleasure dial rather than switching alcohol off completely.
Alcohol can trigger the brain's reward system. When that reward feels weaker, the pull to continue drinking can ease, and some people find it easier to stop after one or two drinks instead of sliding into heavier use. That's the point of the medicine, it helps break the link between drinking and a strong reward signal.
A simple way to picture it is this. Your brain has reward “locks”, and endorphins are one of the keys. Naltrexone puts a blocker in the lock, so alcohol doesn't open that reward pathway as strongly. That doesn't remove choice, and it doesn't erase habit, but it can make cravings less sticky.
Naltrexone only makes sense if opioids are out of the system first. That includes prescribed pain medicines such as codeine, morphine, and tramadol, because the blocker can interfere with them and can trigger withdrawal in someone who's physically dependent. The safety check matters as much as the prescription itself.
Mini answer: naltrexone blocks opioid receptors in the brain, so alcohol feels less rewarding and cravings can become easier to manage.
This explanation of endorphin-driven reward helps if you want the receptor idea broken down even further.
Some people get confused by one point, so it's worth being direct. Naltrexone does not work by making you feel ill if you drink. That's a different medicine strategy. Naltrexone changes reward and craving, which is why it's used as a relapse-prevention tool rather than a punishment tool.
What the Clinical Evidence Actually Shows
The best headline is reassuring, but not magical. A major 2024 systematic review and meta-analysis found that oral naltrexone 50 mg/day was one of the two medicines most consistently linked with better alcohol-consumption outcomes than placebo, based on 118 clinical trials and 20,976 participants [1]. The same review reported an NNT of 18 to prevent one person returning to any drinking, and an NNT of 11 to prevent one person returning to heavy drinking [1].
That means the medicine has real evidence behind it. It also means the effect is useful, but not universal. A treatment with a number needed to treat in that range can help a meaningful number of people, yet it still leaves room for non-response, side effects, and the need for support around it.
A later clinical trial tells the other side of the story. In men with chronic, severe alcohol dependence, naltrexone did not show a significant benefit over placebo at 13 weeks, and it did not reduce drinking days or amount consumed [3]. That matters because it shows the medicine is not equally effective in every AUD population, especially in more severe and long-standing cases.
| Key trial results for oral naltrexone in alcohol use disorder | |||
|---|---|---|---|
| Study / source | Population | Dose and duration | Key result |
| 2024 systematic review and meta-analysis [1] | 118 trials, 20,976 participants | Oral naltrexone 50 mg/day | Better alcohol-consumption outcomes than placebo, NNT 18 for any return to drinking and NNT 11 for heavy drinking |
| Randomised clinical trial [4] | Standard clinical setting patients | Oral naltrexone, trial follow-up | Median time to relapse 90 days with naltrexone vs 42 days with placebo, 33.9% relapsed vs 52.9% on placebo |
| Multisite trial in severe chronic AUD [3] | Men with chronic, severe alcohol dependence | Oral naltrexone with psychosocial therapy, 13 weeks | No significant benefit over placebo, no reduction in drinking days or amount consumed |
What this means for you is straightforward. Naltrexone is best thought of as a targeted tool, not a guarantee. It fits best when there's a clear relapse-prevention or harm-reduction plan, a realistic target, and regular review. It's less convincing as a one-off script handed out with no follow-up.
This balanced discussion of blocking endorphin-driven reward fits neatly with the trial results, because the medicine works through reward control rather than instant abstinence.
Standard and Low-Dose Regimens Explained
The usual oral treatment for alcohol use disorder is 50 mg once daily. Most controlled trials use treatment windows of around 12 weeks to 3 to 4 months, and shorter courses of 12 weeks or less have been linked with better relapse outcomes and lower drinking intensity during active treatment and follow-up [2]. That gives the medicine a practical role, it needs time, and it needs adherence.
Standard oral naltrexone
For most people using it for alcohol relapse prevention, the tablet is the main option. It's simple, predictable, and easy to review. A patient can take it at home, which suits people who can't attend frequent appointments, but that convenience only works if the tablets are taken.
Low-dose naltrexone
Low-dose naltrexone, or LDN, is a different approach. It usually refers to much smaller doses used off-label in other conditions, and it's not the standard evidence-based dose for alcohol use disorder. In alcohol treatment discussions, it may come up because some people are exploring broader naltrexone-based care, but the evidence base you should rely on for AUD is still the standard oral dose [1], [2].
| Standard vs low-dose naltrexone regimens | |||
|---|---|---|---|
| Regimen | Typical daily dose | Main use | Key practical notes |
| Standard oral naltrexone | 50 mg/day | Alcohol relapse prevention | Best supported by the AUD evidence, usually taken daily and reviewed regularly |
| Low-dose naltrexone, LDN | Much smaller off-label doses | Other conditions, not standard AUD care | Sometimes discussed in specialist settings, but not the usual alcohol dependence regimen |
Pharmacist's tip: take the tablet with food if nausea is a problem. That small change often helps people stick with treatment long enough to judge whether it's worth continuing.
Courier Pharmacy's low-dose naltrexone guide explains why LDN gets discussed so often, even though it isn't the usual AUD dose.
The key thing about timing is this. Benefit tends to show itself while the medicine is being taken, so missed doses matter. If someone wants to test whether naltrexone helps them, the first few weeks are usually the most useful period for checking cravings, slips, and drinking pattern.
Side Effects, Interactions and Who Should Not Take It
The trial data on side effects is clear enough to name. Abdominal pain was reported in 8.6% of naltrexone users versus 1.0% on placebo, and headache in 7.5% versus 1.0% on placebo [5]. People can also get nausea, dizziness, and tiredness, and those symptoms can make the first days feel a bit clunky.
The main safety checks
Naltrexone is not for someone currently using opioids. That includes codeine, morphine, and tramadol, plus any opioid-containing cough or pain medicine. It also isn't suitable in acute hepatitis or severe liver disease, and pregnancy needs specialist advice rather than a casual start.
Urgent help is needed if you develop yellowing of the skin, severe abdominal pain, breathing problems, or sudden withdrawal symptoms.
Interactions to check before starting
Some medicines look harmless but can matter a lot here. The biggest issue is hidden opioids in painkillers, cough mixtures, or prescribed medicines after surgery. If a clinician is unsure whether an item contains an opioid, they'll often delay treatment until they've checked.
Pharmacist's tip: read the label of every over-the-counter painkiller and cough remedy before starting. If it includes codeine or any opioid, pause and ask first.
The UK safety guide on naltrexone is worth reading if you want the “who must avoid this” list in one place.
The reassuring bit is that naltrexone is generally described as well tolerated and not intoxicating or sedating [5]. But “generally well tolerated” doesn't mean “ignore symptoms”. A quick message to the prescriber early on is better than trying to push through side effects that could have been managed.
Real-Life Scenarios From a UK Pharmacist
A woman in Manchester tells me she doesn't want to stop all contact with alcohol straight away. She wants Friday nights to stop turning into two-day hangovers, but she can't commit to daily groups because her children's bedtime is chaos. In that case, naltrexone can sit alongside psychosocial support as a practical relapse-prevention tool, not as a judgement on whether she's trying hard enough.
A shift worker in Derby gives a different picture. He drinks heavily after night shifts because the end-of-shift crash has become a cue, almost like a routine. With regular review, naltrexone may help weaken that cue-reward link, while the prescriber and patient work on sleep, food, and timing patterns that keep the cycle going.
These examples matter because treatment lives inside ordinary life. A medicine only helps if it fits around school runs, late finishes, family meals, and the random mess of real schedules. That's why a simple plan is better than an ambitious one nobody can keep.
Real-world rule: if the medicine doesn't fit your routine, it won't help for long.
In both cases, the diary matters. A few notes on cravings, slips, and drinking triggers can tell the prescriber more than a vague memory at follow-up. That makes the next adjustment more sensible, whether that means continuing, changing strategy, or adding more support.
How to Get Naltrexone in the UK and What Monitoring Looks Like
In the UK, there are two realistic routes. You can go through your GP or a specialist alcohol service, or you can use a private online consultation with a GPhC-registered pharmacy such as Courier Pharmacy, where a prescriber reviews a secure questionnaire and checks whether treatment is safe and appropriate. The pathway is still medical, even if it starts online.
That questionnaire is there for a reason. It checks alcohol intake, opioid medicines, liver history, and other medicines before anyone approves treatment. If naltrexone is suitable, monitoring usually includes baseline and follow-up liver function tests, plus a review of how well the medicine is being taken and whether cravings are changing.
If drinking happens again, that doesn't automatically mean failure. It means the plan needs review. The prescriber may look at timing, dose adherence, side effects, or whether the original target was realistic enough.
Pharmacist's tip: be completely honest about how much you drink right now on the questionnaire. Safety depends on the prescriber seeing the full picture, not the version that sounds tidiest.
Courier Pharmacy also offers free follow-up calls in some treatment pathways, which helps keep the medicine tied to review rather than left to drift. That kind of support matters more than people expect, because naltrexone works best when someone checks in and adjusts the plan if needed.
Key Takeaways and Common Questions
Five practical takeaways
- Naltrexone can reduce relapse risk, but it works best with follow-up.
- The standard evidence-based dose is 50 mg/day for oral treatment.
- It is not suitable with opioid medicines in your system.
- Side effects are usually manageable, but abdominal pain and headache do happen.
- UK access is possible through NHS care or a regulated private pharmacy route.
FAQ 1. Can I take opioid painkillers while on naltrexone?
No, not safely unless a clinician has specifically planned and supervised the switch. Naltrexone blocks opioid medicines and can cause withdrawal if opioids are already in your system. Always check codeine, tramadol, morphine, and combination cough or pain remedies first.
FAQ 2. Does naltrexone damage the liver?
It can be used safely in many people, but liver checks matter because the medicine needs monitoring. People with acute hepatitis or severe liver disease should not start it without specialist advice. That's why baseline and follow-up tests are part of good care.
FAQ 3. What happens if I drink while taking it?
The medicine doesn't make alcohol instantly unsafe in the way some other treatments can, but it may be less effective if you keep drinking heavily. The key risk is that the underlying pattern continues, so the prescriber should know if drinking is still happening. Honest follow-up helps shape the next step.
FAQ 4. How long should treatment last?
Many controlled trials use around 12 weeks to 3 to 4 months, and response is often judged in that window [2]. Some people need a shorter or longer plan depending on their goals and progress. The right duration is the one that matches the treatment target and your review plan.
FAQ 5. Can I stop as soon as I feel better?
You can, but it's better to agree that decision with the prescriber first. If the medicine is helping, stopping too early can remove that support just when habits are starting to shift. A planned review is safer than a sudden stop.
FAQ 6. Is this article a substitute for medical advice?
No. It's informational only and can't replace a proper consultation. If you're unsure about opioid medicines, liver disease, or withdrawal risk, speak to a clinician before starting anything.
For more reading, look at the related Sinclair Method, LDN, and safety pages on Courier Pharmacy's site.
Courier Pharmacy can help you explore whether naltrexone is suitable through a regulated online consultation, with prescriber review and follow-up built into the process. If you're weighing up alcohol relapse prevention and want a UK route that keeps safety front and centre, visit Courier Pharmacy to read more about the options and start a clinical assessment.


