What Is Sleep Apnea Treatment: A UK Guide 2026
Discover what is sleep apnea treatment in the UK, from CPAP to surgery, and how to access care.

SEO brief
Primary keyword: what is sleep apnea treatment
Secondary keywords: sleep apnoea treatment, CPAP, oral appliance, sleep study, OSA treatment, UK sleep clinic
Search intent: Understand treatment options and next steps in the UK
Target reader: UK adults, carers, and sleep-curious readers
Product/service mention (if any): Courier Pharmacy, mentioned at the end only
Internal links available: sleep conditions, weight loss, treatment, melatonin, online pharmacy
What is sleep apnoea treatment? It's the set of steps used to keep your airway open at night, cut down breathing pauses, and help you feel safer and more rested. The path starts with a proper sleep study, then the treatment choice depends on how severe the problem is and whether you can tolerate a mask, a device, or a lifestyle plan.
If you've been nudged awake for snoring, wake up exhausted, or feel sleepy at the wrong times, you're not alone. The good news is that sleep apnoea treatment is not one single gadget. It's a stepped pathway, and this guide walks through the whole thing in plain English, from mild cases to CPAP, devices, surgery, and UK access routes.
Five key takeaways
- Sleep apnoea treatment starts with a diagnosis, not guesswork.
- CPAP is the main first-line treatment for moderate to severe OSA in UK guidance.
- Lifestyle changes can be real treatment, especially in milder cases.
- If CPAP doesn't suit you, there are alternatives, including oral devices, surgery, and nerve stimulation.
- Getting help early matters, especially if sleepiness affects driving or work safety.
Understanding Sleep Apnoea and Why Treatment Matters
A partner who keeps nudging you awake. A shift worker fighting sleep in the car park before the drive home. A gym-goer who trains hard but still feels drained by lunchtime. Those are the kinds of clues that often lead people to ask what is sleep apnea treatment, because the issue reaches far beyond snoring alone.
Obstructive sleep apnoea, or OSA, happens when the upper airway keeps collapsing during sleep. The airway narrows or shuts, breathing pauses, and sleep gets broken up again and again. UK sleep services use the apnoea-hypopnoea index, or AHI which is explained in our sleep conditions guide, which measures how often these events happen per hour, and OSA is commonly defined by breathing pauses lasting more than 10 seconds and occurring at least 5 times per hour. That objective measurement matters, because treatment decisions are based on the sleep study, not just on how loud the snoring sounds. [1]

Practical rule: if the airway keeps collapsing, the treatment has to keep it open.
Why the severity matters
UK guidance usually talks about mild, moderate, and severe OSA because the treatment choice changes with severity. Mild cases may start with lifestyle work or an oral device, while CPAP is the standard first-line option for moderate to severe OSA and for some people with mild disease plus relevant comorbidities or cardiovascular risk. NHS Inform also notes that people with moderate to severe OSA usually need CPAP, while mandibular advancement devices are mainly used for mild OSA or when CPAP is not tolerated. [1][2]
The point is simple. Snoring is a symptom, not the diagnosis. The core issue is airway collapse, oxygen dips, broken sleep, and the strain that places on day-to-day life. Once that is clear, the rest of the pathway makes more sense.
What a treatment plan is trying to do
Good treatment has one aim. It keeps the airway open enough that breathing stays steady through sleep. Clinical sources describe CPAP as a steady column of air that splints the airway open, which directly tackles the collapse that defines OSA. [1][2]
That is why treatment can look different from person to person. One reader may need a mask every night. Another may do well with side-sleeping, weight loss, or a jaw device. A third may need specialist surgery or a nerve implant if standard options fail. The pathway is stepped for a reason, and severity decides the first move.
Getting Diagnosed With a Sleep Study in the UK
Before any mask, oral device, or prescription, the diagnosis needs to be objective. In the UK, that usually means a sleep study, because symptoms alone can be misleading. Two people can both snore loudly, but only one may have clinically important OSA.
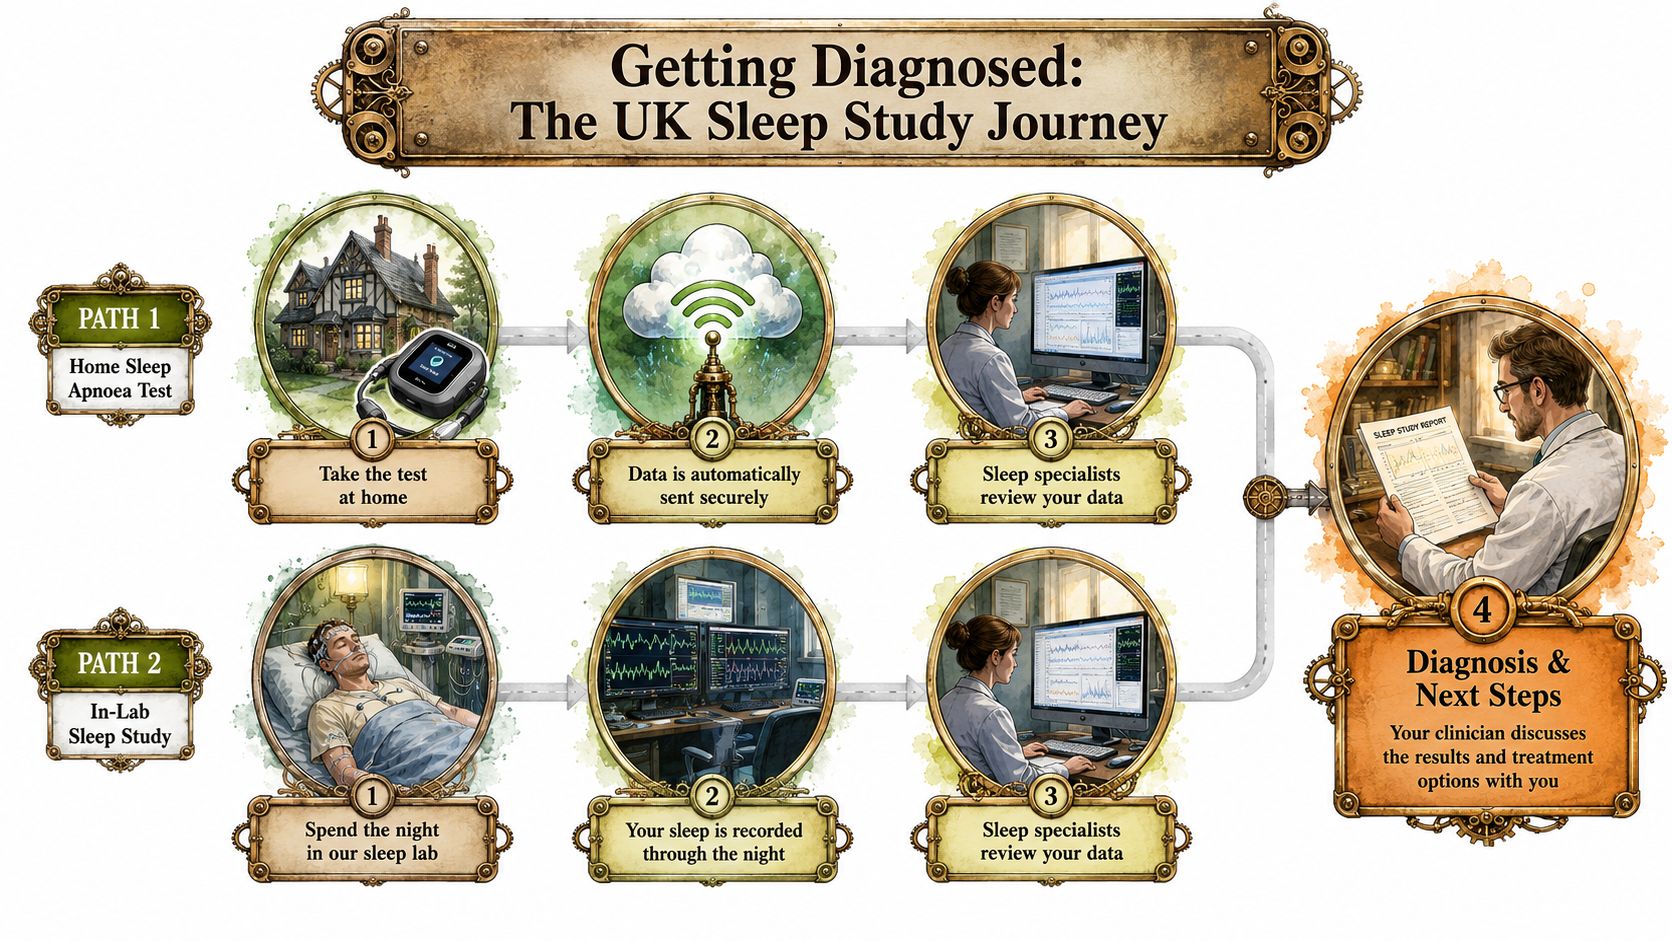
Home test or sleep clinic study
For many adults, the first option is a home sleep apnoea test. It's a small device worn overnight at home, and it usually measures things like airflow, oxygen levels, breathing effort, and sometimes heart rate. The other route is a full polysomnography in a sleep clinic, which gives a more detailed picture of sleep and breathing patterns. [1]
A home test often suits straightforward suspected OSA. A full lab study is more useful when the picture is messy, when other sleep disorders may be involved, or when the clinician needs a deeper look. In both cases, the report helps match treatment to severity rather than relying on guesswork.
| Test type | What it does | Common setting | What it helps with |
|---|---|---|---|
| Home sleep apnoea test | Records breathing and oxygen data overnight | Your own bed | Straightforward suspected OSA |
| Polysomnography | Records sleep and breathing in detail | Sleep clinic | More complex cases or unclear symptoms |
How the UK pathway usually starts
On the NHS, a GP may screen for red flags and arrange a referral. In private care, a clinician can often move more quickly to testing. Some UK-regulated online pathways also use questionnaires to decide whether a home test is clinically appropriate, then a human prescriber reviews the result before any treatment is offered. That makes the process faster, but it still stays medical rather than automated.
Featured-snippet style answer:
Do I need a sleep study to start treatment? In most cases, yes. A sleep study helps confirm OSA, grade the severity, and choose the right treatment safely. [1]
Red flags that need urgent review
Seek medical help sooner if you have:
- Severe daytime sleepiness, especially if you might fall asleep while driving
- Breathing pauses noticed by others
- Morning headaches with marked exhaustion
- Known heart or blood pressure problems with suspected OSA
- Sudden worsening symptoms
If sleepiness is affecting driving, don't wait for a routine referral. Safety comes first.
Lifestyle Changes That Count as Real Treatment
A tired patient who snores loudly, wakes unrefreshed, and is waiting for a sleep clinic appointment still has options that can make a real difference before any machine or device is fitted. Lifestyle treatment gets treated like background advice far too often. For mild OSA, though, it can be part of the real treatment plan, not an afterthought. Mayo Clinic lists weight loss, quitting smoking, sleeping on your side, and avoiding alcohol for 4 to 6 hours before bed as practical management steps. [4] If weight is part of the picture, a structured approach such as weight-loss support may help alongside other changes.
The airway responds to everyday habits
Extra weight can narrow the upper airway and make collapse more likely, which is why weight change is one of the first lifestyle tools clinicians consider. Alcohol near bedtime can relax airway muscles, so breathing pauses are easier to trigger. Side-sleeping can help some people because the airway tends to behave better than it does on the back. Smoking also irritates the airway, which can make things worse. [4]
These changes work like adjusting the parts of a hinge so a door stops sticking. They do not cure every case, and they are not a replacement for every other therapy. They are one part of the plan, especially when OSA is mild or when you are waiting for another treatment to start.
A realistic UK example
A 38-year-old shift worker comes in tired, snores heavily, and wakes unrefreshed. His sleep test shows mild OSA. Over time, he loses 8 kg and starts side-sleeping with a simple positional aid. His AHI falls from 14 to 7 events per hour, and he feels more human on early shifts.
That kind of improvement will not happen for everyone, and it does not mean the condition has vanished. It does show why lifestyle work deserves a proper place in the pathway.
Pharmacist's tip: if you are making lifestyle changes, ask for a repeat sleep test or follow-up plan. Data makes progress easier to prove, and it helps your clinician decide whether you still need another treatment layer.
A few habits that are worth doing well
- Weight change: even modest loss may help airway stability if excess weight is part of the problem.
- Side-sleeping: use pillows or positional aids if you keep rolling onto your back.
- Alcohol timing: keep alcohol away from the 4 to 6 hour pre-bed window.
- Smoking support: ask for stop-smoking help if nicotine is part of your routine.

CPAP APAP BiPAP and Oral Devices Compared
If you only remember one thing from this section, make it this. CPAP pushes one steady pressure, APAP adjusts within a range, BiPAP uses two pressures, and mandibular advancement devices hold the jaw forward. That's the basic difference, and it helps a lot when you're reading clinic letters or discussing options with a prescriber.
Comparing the main devices
| Device | How it works | Best for | Main trade-off |
|---|---|---|---|
| CPAP | Delivers a fixed stream of air to keep the airway open | Moderate to severe OSA, and some mild cases with risk factors | Mask comfort and regular nightly use |
| APAP | Auto-adjusts pressure through the night | People whose pressure needs vary | Still uses a mask, so comfort matters |
| BiPAP | Uses higher pressure on inhale and lower pressure on exhale | More complex cases or higher pressure needs | More complex setup |
| Mandibular advancement device | Moves the lower jaw forward to widen the airway | Mild OSA or when CPAP isn't tolerated | Needs dental suitability and careful fitting |
Who tends to suit what
In UK practice, CPAP is the anchor treatment for clinically significant OSA. That's because it directly prevents airway collapse, which is the core problem. APAP can be useful when a fixed pressure feels too blunt, while BiPAP may suit people who need a different pressure profile.
Oral devices are different. They don't blow air. They change jaw position, which can open the airway enough for mild disease or for people who just can't get on with a mask. That makes them a sensible alternative in the right patient, not a second-rate version of CPAP.
Featured-snippet style answer:
Is CPAP always the best treatment? No. CPAP is the usual first-line option for moderate to severe OSA, but oral devices, lifestyle change, surgery, and other therapies may suit some people better. [1][2]
A quick way to think about it
- CPAP: best for steady, reliable airway splinting
- APAP: best when pressure needs vary through the night
- BiPAP: best when exhaling against pressure is difficult
- Oral device: best when mild disease or mask intolerance is the main issue
Pharmacist's tip: if a machine feels wrong in the first week, don't assume you've failed treatment. Mask fit, humidification, and pressure review often make a big difference.
Courier Pharmacy treatment options can help readers see how prescription pathways fit into the broader UK sleep apnoea picture.
Surgery and Nerve Stimulation When Devices Are Not Enough
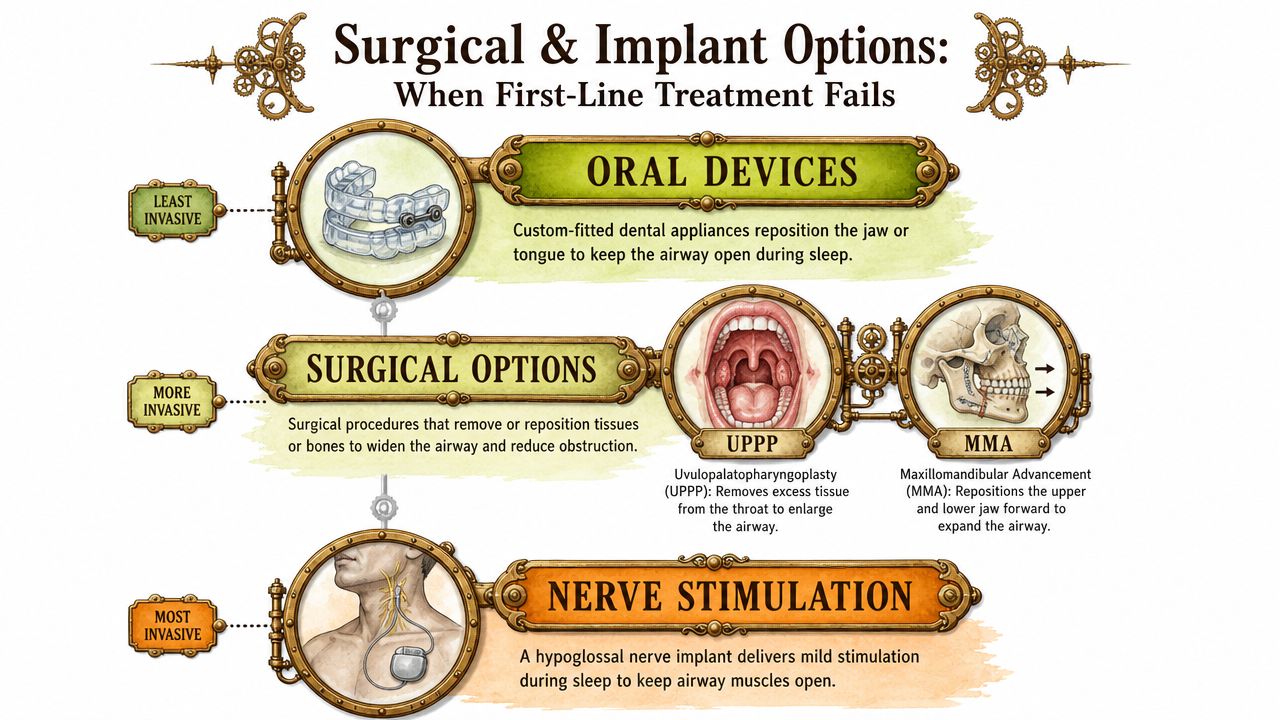
Not everyone gets on with a mask or an oral device. Some people can't tolerate them. Others need something stronger because the anatomy or the severity makes standard options less effective. That's where specialist surgery and nerve stimulation come in.
The main specialist options
Uvulopalatopharyngoplasty, or UPPP, removes or reshapes tissue at the back of the throat to widen the airway. Tonsillectomy and adenoidectomy can help when enlarged tissue is part of the problem, especially with large tonsils. Bariatric surgery may help when obesity is the main driver and other weight measures haven't worked well enough. [3]
These are not casual add-ons. They need specialist assessment, and they're usually considered when first-line treatment hasn't been enough. The question isn't, “Is surgery available?” It's, “Does this person's airway anatomy and overall health make surgery the right tool?”
Hypoglossal nerve stimulation
A newer option is implantable hypoglossal nerve stimulation, or HNS. The implant stimulates the nerve that helps move the tongue, which keeps the airway more open during sleep. A major summary of the evidence reports that HNS reduced the median AHI by 68% at 12 months, from 29.3 events per hour to 9.0 events per hour in selected patients. [3]
That result matters, but it doesn't mean HNS is for everyone. It's for carefully chosen patients, often those who can't tolerate CPAP and meet specialist criteria. CPAP still anchors the evidence base for most adults with clinically important OSA. [1][3]
When a referral is worth asking for
Ask about ENT or sleep specialist review if:
- You can't tolerate CPAP despite proper support
- Your anatomy suggests a local obstruction
- Large tonsils are clearly part of the picture
- Weight is driving the condition and other measures have stalled
- You want to know if HNS eligibility is realistic
Surgery is a tool, not a fallback for failure. In the right patient, it can be the best next step.
Oxygen, Medications and Daytime Sleepiness Management
Some people still feel sleepy even after the main airway treatment is in place. Others have oxygen drops that need a more specific plan. Adjunct care comes in, and it has to be used carefully because it won't fix airway collapse on its own.
What fits where
Supplemental oxygen may be used selectively when desaturation is the dominant issue, but it doesn't replace airway treatment. Positional trainers and vibrating wearables can help remind some people to stay off their back. Weight-management medicines, including GLP-1 options, may support treatment when obesity is driving OSA, though they're part of a wider plan rather than a stand-alone fix. [4]
For daytime sleepiness, some clinicians consider wakefulness-promoting medicines such as modafinil when sleepiness remains despite treating the underlying OSA. That's a specialist decision, because the first job is still to treat the airway problem properly.
What does not treat OSA
Melatonin, herbal sleep aids, and over-the-counter stimulants don't fix airway collapse. They might change how sleepy you feel, but they don't stop the airway from closing. The internal link on whether melatonin is safe every night is useful reading if you're tempted to self-treat the tiredness rather than the cause.
Pharmacist's tip: caffeine tablets and “stay awake” products are not a substitute for OSA treatment. If you need them to keep going, the underlying sleep problem still needs proper review.
A sensible way to think about adjuncts
- Use oxygen only when a clinician has said it fits your pattern.
- Use positional aids if back-sleeping clearly worsens symptoms.
- Use weight-management support if excess weight is part of the cause.
- Use wakefulness medicines only after the core airway issue is addressed.
How to Access Sleep Apnoea Care in the UK
The UK route usually starts with your GP. That makes sense if you snore heavily, wake unrefreshed, or have daytime sleepiness. The GP can check for urgent red flags and refer you into an NHS sleep clinic where appropriate.
NHS, private, and online routes
If you want the NHS route, expect a referral pathway and local waiting times. If you want a faster answer, a private home sleep test may be the simplest next move. Some UK-regulated online pharmacies also use secure questionnaires and human prescriber review to support suitable follow-up care, weight-management help, and related treatment options. GPhC registration matters here, because it shows the pharmacy is operating under UK regulation.
The choice depends on speed, complexity, and what's clinically suitable. A straightforward suspected case may work well with a home test. A more complex picture may need a sleep clinic. Either way, the goal is the same, a proper diagnosis and a treatment match.
What you can do tonight, this week, and this month
- Tonight: stop driving if you're dangerously sleepy.
- This week: book a GP appointment or arrange an appropriate sleep assessment.
- This month: get your sleep study result, then discuss treatment choices.
- Alongside that: keep a note of snoring, waking, headaches, and daytime sleepiness.
Courier Pharmacy's online pharmacy service is a relevant option for readers who want regulated, discreet support alongside wider sleep and wellbeing care.
Summary and Frequently Asked Questions
Sleep apnoea treatment starts with a sleep study, because the severity drives the plan. CPAP is the main first-line option for moderate to severe OSA, while milder cases may start with lifestyle measures or an oral device. If those don't work, specialist options like surgery or nerve stimulation may be considered. If you're too sleepy to drive safely, get medical help sooner rather than later.
FAQ
What happens if CPAP stops working?
First, check the basics, mask fit, pressure settings, and whether you're still using it enough each night. If problems continue, your sleep team may look at APAP, BiPAP, an oral device, or a specialist review.
Are oral devices as good as CPAP?
They can work well for the right person, especially in mild OSA or when CPAP isn't tolerated. CPAP is still the standard first-line treatment for moderate to severe disease.
Can children have sleep apnoea?
Yes, children can have OSA, and enlarged tonsils or adenoids are a common reason. They need paediatric assessment rather than adult-style self-treatment.
How long does sleep apnoea treatment last?
It often lasts long term, because OSA usually doesn't disappear overnight. Some people improve enough with weight loss or surgery to change treatment, but many need ongoing support.
Can lifestyle changes replace CPAP?
Sometimes in mild cases, but not always. Lifestyle changes are best seen as part of the treatment plan, not a universal replacement.
What if I keep waking up exhausted even with treatment?
That needs review. The issue may be residual sleepiness, poor mask fit, another sleep problem, or a treatment that needs adjusting.
Do I need urgent help if I'm falling asleep at work?
Yes, especially if driving, operating machinery, or caring for someone is involved. Sleepiness at the wrong time is a safety issue, not just a nuisance.
If you want a regulated, UK-based route for sleep-related support, treatment guidance, and discreet follow-up care, visit Courier Pharmacy and explore the options that fit your situation. They can help you think through next steps without making sleep apnoea treatment feel like a maze.


