Why Is Naltrexone Controversial? a UK Guide
Why is naltrexone controversial? Explore the evidence gaps, mixed trial results, and access issues affecting the medication in the UK.

SEO brief
- Primary keyword: why is naltrexone controversial
- Secondary keywords: naltrexone UK, low-dose naltrexone, alcohol dependence treatment, opioid dependence, naltrexone side effects, Sinclair Method
- Search intent: patient-friendly explanation and UK access guidance
- Target reader: UK adults, carers, and health-curious readers
- Product/service mention: prescriber-led naltrexone and LDN consultations where suitable
- Internal links available: Courier Pharmacy pages on the Sinclair Method, low-dose naltrexone, fibromyalgia, and side effects
Naltrexone is prescribed to less than 0.5% of eligible people in the UK, even though it has been clinically available for decades and evidence of benefit exists. That gap is a big reason why is naltrexone controversial. The debate sits at the point where mixed trial results, low real-world uptake, and uncertainty around low-dose use all meet.
For patients, that can feel frustrating. You may hear that the medicine helps, then hear it doesn't, then discover it's hard to get in routine care. If you're trying to make sense of that, this guide breaks it down in plain English and keeps the focus on what matters in a consultation.
Why Is Naltrexone Controversial
A University of Manchester review found that naltrexone is prescribed to less than 0.5% of people eligible for it in the UK, while 7,697 alcohol-specific deaths were recorded in 2017, equal to 12.2 deaths per 100,000 population. That gap is a big reason why naltrexone is controversial. Supporters see a treatment that may help more people than it currently reaches, while critics point to mixed uptake and the uncertainty that can surround prescribing in everyday practice. Manchester review

Five practical points to keep in mind
- It's a relapse-prevention medicine, not a cure. It can reduce reward and craving, but it does not address the wider causes of addiction on its own.
- The evidence is mixed. Some trials look encouraging, others do not, so people can read the research and come away with different impressions.
- UK access is patchy. Many eligible people never get offered it, which makes the debate as much about service delivery as about the medicine itself.
- Low-dose use sits in a grey area. That is part of the discussion around private prescribing and why some patients hear about it only through informal routes.
- A good consultation matters. The right dose, timing, and monitoring can change the experience completely, especially when other medicines or conditions are involved.
Practical rule: if a medicine looks promising in papers but rarely reaches patients, the controversy is often about access as much as science.
For many people, the hardest part is not deciding whether naltrexone exists. It is working out whether it fits their situation, their history, and their current treatment plan. For a UK overview of how naltrexone is discussed in alcohol recovery, see this Sinclair Method guide.
What Naltrexone Is and How It Works
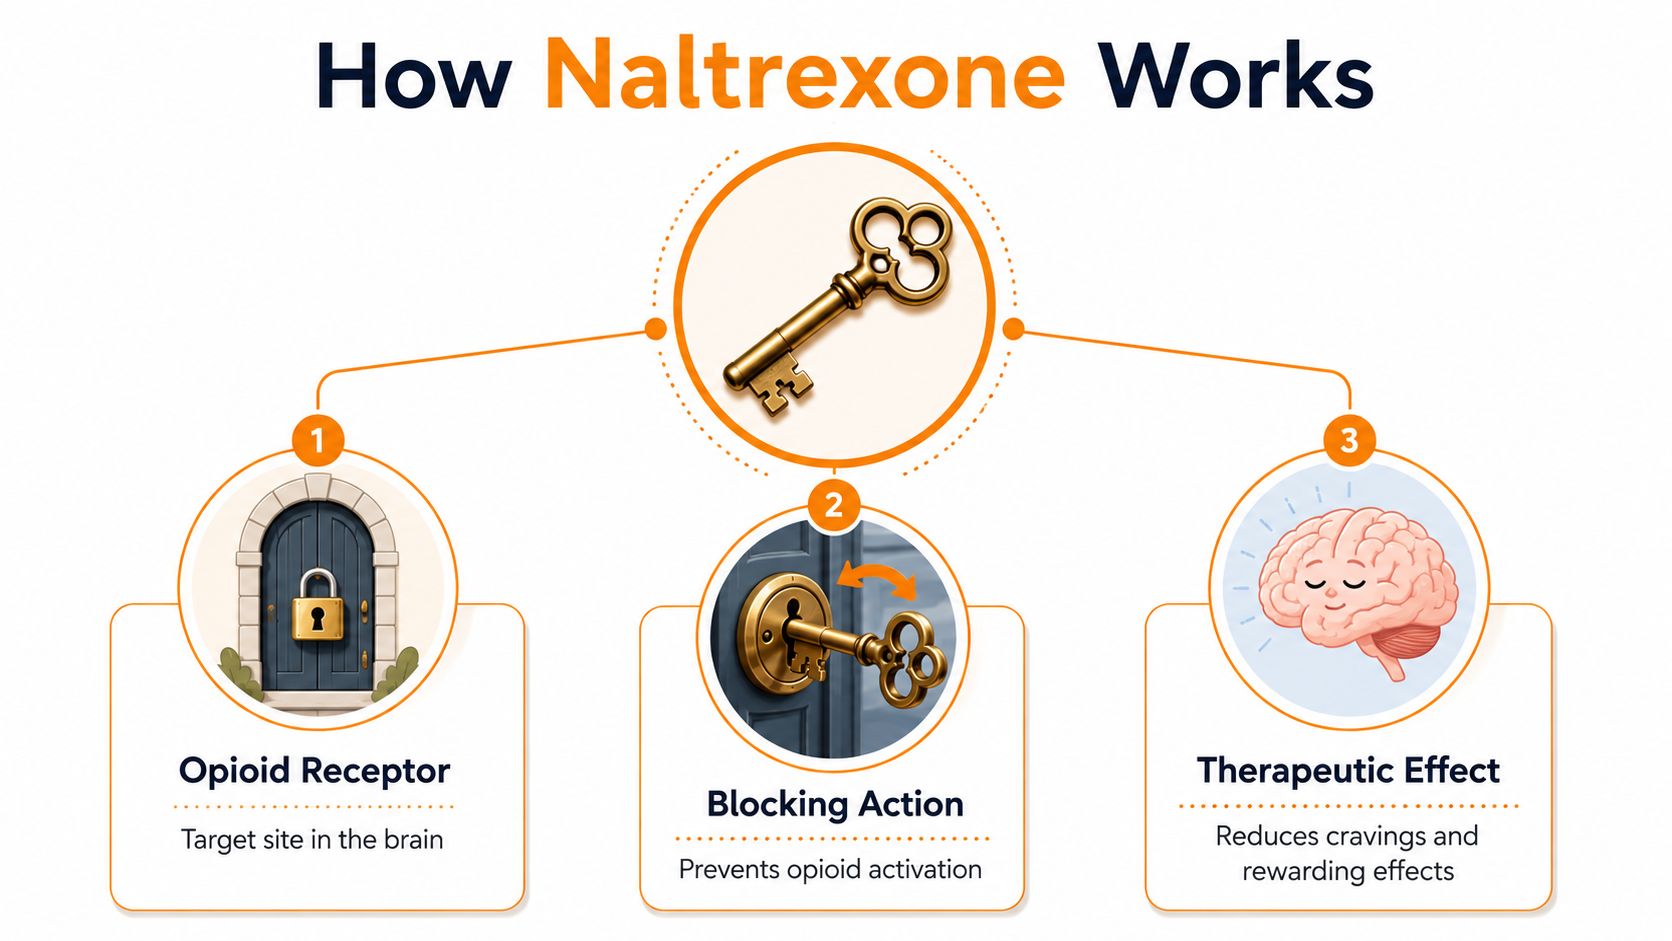
Naltrexone is an opioid receptor antagonist. In plain language, it sits on the same receptor sites that opioids use and blocks them from switching on. The idea is straightforward, like a key that fits the lock but does not open the door.
What that means in practice
For alcohol dependence, naltrexone can reduce the rewarding effect of drinking and help lower cravings. For opioid dependence, it blocks opioid effects and can help prevent relapse after detoxification. It supports recovery, it does not create recovery on its own.
A shift worker with unpredictable evenings might use naltrexone so drinking feels less rewarding after work. A person in early recovery might use it to dull the pull of triggers on a difficult weekend. In both cases, the medicine is only one part of a wider plan.
Approved uses and expectations
In the UK, the discussion usually centres on two licensed areas:
- Alcohol dependence
- Opioid dependence
That distinction matters because patients sometimes expect a quick fix. Naltrexone is better understood as a relapse-prevention tool, not a cure. If someone stops taking it, the protection goes with it.
Pharmacist's tip: ask how the medicine is meant to help in your exact situation. A clear goal, like preventing relapse or reducing heavy drinking, makes the plan easier to judge.
For readers looking at low-dose prescribing pathways, this page on how LDN works gives a useful extra overview.
The Evidence and Effectiveness Debate
The debate grows because the study results do not all point the same way. Some trials show benefit, others find little or no meaningful difference from placebo. That is why different readers can look at the same medicine and reach opposite conclusions.
Naltrexone evidence at a glance
| Condition | Positive finding | Limitation or negative finding |
|---|---|---|
| Alcohol dependence | One large trial reported 73.7% good clinical outcomes with naltrexone versus 58.2% with placebo, about a 15 percentage point difference PMC review | A large New England Journal of Medicine study found no evidence that it prevented relapse or reduced drinking in men with chronic, severe alcohol dependence NEJM trial |
| Opioid dependence | Some analyses show favourable point estimates for treatment outcomes NEJM trial discussion | A Cochrane review found oral naltrexone was no better than placebo or no pharmacological treatment for several key outcomes, with treatment retention at 28% PMC review |
Why readers get conflicting messages
A single positive trial can sound convincing. So can a single negative trial. The fair reading is more cautious. Naltrexone appears to help some people in some settings, but not every group responds in the same way.
The medicine is not the same as the message around it. One person's good result does not erase another person's poor response.
The picture gets even harder to read because evidence from alcohol use disorder does not transfer neatly to opioid dependence. In opioid care, the need for complete abstinence before starting treatment makes uptake harder, and that barrier affects real-world results. In the UK, that matters as much as the trial tables. A medicine can look useful on paper and still reach very few eligible patients if access is slow, uneven, or tied up in local prescribing rules. For readers who want the background on how low-dose use developed, this article on the evolution of low-dose naltrexone gives a helpful overview.
Why Low-Dose Naltrexone Raises Questions
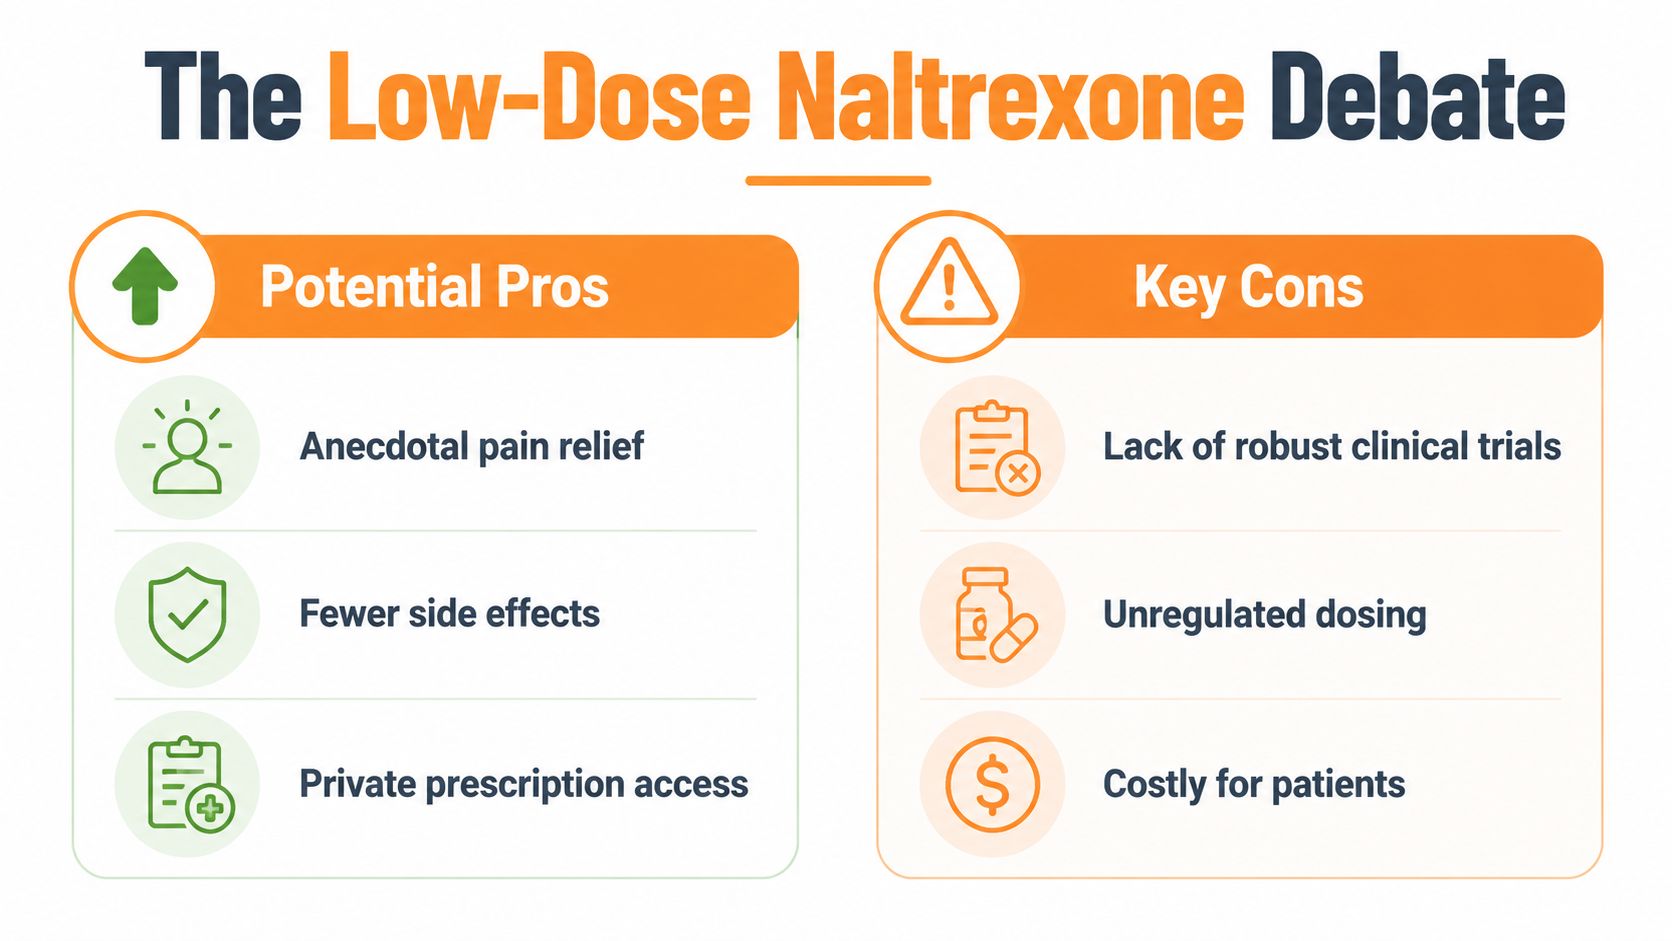
Low-dose naltrexone, or LDN, creates a separate set of questions because it sits outside the strongest evidence base. A review focused on LDN says there is no FDA-approved use of naltrexone at any dose for chronic pain or inflammatory disease, and that the clinical evidence is still very preliminary. That does not mean it never helps anyone, but it does mean the evidence is not settled.
Why fibromyalgia often comes up
Fibromyalgia is the best-studied use for LDN, yet the evidence is still limited. A systematic review concluded that the strength of evidence from randomised controlled trials is low, with only low-grade evidence that LDN reduces pain and improves quality of life in women. Other evidence summaries say it is still not possible to judge clearly whether LDN is effective or safe across different patient groups. LDN review
That is why some clinics and patients feel hopeful, while many clinicians remain cautious. The treatment makes biological sense on paper, but that is only the starting point. A plausible mechanism is like a map with the roads drawn in, it does not prove the journey will be smooth for every person. People can also mistake an individual story of improvement for settled evidence.
Why the private market complicates things
LDN has become popular in private care partly because people with long-term symptoms often feel they have run out of standard options. That reaction is understandable. It can also create a gap between what patients hope for and what the evidence can support safely.
The result is a medicine that many people discuss with confidence, even though the underlying data remain thin. That makes shared decision-making especially important, especially when people are paying privately and hoping for an answer that standard care has not given them. For a focused patient guide, Courier Pharmacy's fibromyalgia and LDN information may be a helpful starting point.
In the UK, the bigger question is not just whether LDN might help in theory. It is why a medicine with some promise still reaches so few people who could be considered for it. That access gap is part of why the debate around LDN keeps going. It is not only a question of evidence, it is also a question of who gets the chance to try treatment.
Safety Concerns and Prescribing Barriers
A medicine can be effective and still be awkward to use safely. Naltrexone is a good example. If a person has opioids in their system, it can trigger rapid withdrawal, and if they try to override the opioid blockade, they can put themselves at serious risk. Safety materials also warn about overdose risk if opioids are used after stopping naltrexone, and caution is advised in acute hepatitis, hepatic failure, or severe renal impairment. Safety review
Why doctors hesitate
One reason naltrexone still divides opinion is plain caution. The Manchester review found no evidence of serious side effects linked to naltrexone, yet many doctors still worry about liver toxicity. That mismatch between concern and evidence matters in everyday prescribing. If a prescriber is uneasy, the patient may never get even a monitored trial of treatment. Manchester review
There is also a practical issue that is easy to miss. Naltrexone only works if people keep taking it, and the early FDA approval note for heroin addiction made clear that the drug does not reinforce compliance on its own. In other words, the tablet is only part of the picture. The plan around it matters too. Compliance note
Two common real-world scenarios
A patient restarts naltrexone too soon after opioid painkillers and gets severe withdrawal. That is not a theoretical problem. It is why timing, medicine history, and opioid-free checks need to be sorted carefully before the first dose.
A GP wants to help, but remains worried about liver safety despite reassuring evidence. The patient leaves without treatment, even though the medicine might have been suitable with proper monitoring. That is how a prescribing barrier turns into a missed opportunity.
For side-effect questions around lower-dose use, this guide to low-dose naltrexone side effects gives a helpful overview.
Pharmacist's tip: never start naltrexone after opioids without checking the timing carefully. If there is any doubt, speak to the prescriber first.
Navigating Naltrexone Access in the UK
The access problem is where the controversy becomes concrete. A medicine can look helpful on paper, yet if eligible people rarely get offered it, the argument stops being theoretical. In the UK, uneven treatment routes, prescriber unfamiliarity, and stigma around medication-assisted care all shape who reaches treatment.
What to ask before starting
If you're considering naltrexone or LDN, ask direct questions. Clear answers usually point to safer prescribing, and they also show whether the prescriber has a settled plan rather than a vague idea.
- What is the treatment goal? Ask whether the plan is relapse prevention, craving reduction, or symptom support.
- What checks do I need first? Ask about opioid use, liver checks, and any other medicines.
- Who reviews me if I have problems? Follow-up matters as much as the first prescription.
Pharmacist's tip
- Ask about experience. Find out whether the prescriber has treated your condition before.
- Ask about monitoring. You should know what gets checked, and when.
- Ask about support. A medicine works better when you know who to contact if things change.
One route some UK patients use is a supervised consultation model with prescriber review, especially where LDN or alcohol-use treatment is being considered. Courier Pharmacy offers that kind of structured consultation for suitable patients, with monitoring built into the process. That does not remove clinical judgement, but it does make the pathway clearer and easier to understand.
Real-life example
A busy parent with alcohol cravings may want a discreet option and a plan that fits school runs, work, and sleep debt. A shift worker may need a prescriber who understands irregular routines and missed doses. In both cases, access is not just about getting a prescription, it is about getting one that can be used safely.
One extra issue is the UK access gap itself. A medicine can be licensed or discussed in specialist settings, yet still never reach the people who might benefit because the route in is too unclear. That can leave patients doing a lot of the work themselves, asking around, comparing services, and trying to work out whether anyone will prescribe and monitor it properly.
Practical rule: if the plan feels vague, keep asking until it doesn't. A good consultation should leave you knowing what happens next.
What to Discuss with Your Prescriber
A good conversation with your prescriber should cover the medicine, the risk, and the follow-up. If you're thinking about naltrexone, bring a short list of questions and ask them one by one. That usually makes the appointment calmer and more useful.
Questions worth taking in
- Is naltrexone suitable for my condition? The answer may differ for alcohol dependence, opioid dependence, or off-label LDN use.
- Do I need any tests first? Ask about liver checks and whether any medicines could interact.
- How long should I take it? The plan should have a review point, not an endless repeat.
- What side effects should I watch for? Ask what is expected and what needs urgent help.
- What if I use opioids for pain? This is especially important if you have surgery or chronic pain.
- Who do I contact if I miss doses or feel unwell? A fallback plan matters.
Summary
Why is naltrexone controversial? Because the evidence is mixed, access is poor, and low-dose use still lacks proof.
It can help some people, especially when used for the right reason and with proper support.
It can also cause harm if started at the wrong time after opioid use.
Many eligible people in the UK still never get offered it.
Low-dose naltrexone is promising for some, but the evidence base is still thin.
The right consultation should cover goals, checks, follow-up, and safety.
This article is for information only, not a substitute for medical advice. Always speak to a qualified prescriber or pharmacist about your own situation.
FAQs
Is naltrexone addictive?
No, naltrexone is not an opioid and it doesn't cause opioid-style dependence. It blocks opioid receptors rather than activating them. That said, it should still be taken exactly as prescribed.
What's the difference between regular naltrexone and low-dose naltrexone?
Regular naltrexone is used in standard treatment pathways, mainly for alcohol dependence and opioid dependence. Low-dose naltrexone uses much smaller amounts and is often discussed for chronic pain or inflammatory symptoms. The evidence and intended use are not the same.
How long does naltrexone take to work?
Some people notice changes fairly early, but the effect depends on the condition being treated and how the medicine is used. It's not a quick fix in the way a painkiller can be. Your prescriber should explain what a realistic timeline looks like for you.
Can I take naltrexone with other medicines?
Maybe, but it depends on the medicine. The biggest concern is any opioid, including pain relief or medicines used around surgery. Always tell the prescriber and pharmacist everything you take.
What should I do if I get side effects?
Contact the prescriber or pharmacist if the effects are mild but worrying. Seek urgent help if you may have taken opioids, if you feel severely unwell, or if you have symptoms that suggest a serious reaction. Don't restart treatment on your own after stopping.
Can I get LDN consultations in the UK?
Yes, some UK services offer supervised LDN consultations, but suitability depends on your condition and medical history. A proper review should include safety checks, dosing guidance, and follow-up. Avoid any service that skips these steps.
Does naltrexone help everyone with alcohol dependence?
No. The evidence shows benefit for some people, but not for everyone. That's one reason the medicine remains controversial, even though many clinicians still consider it useful.
How this content was created
This article was written from the verified data provided here, then checked against the linked primary sources and UK-facing pharmacy information. It was structured to keep the science clear, the safety advice practical, and the wording suitable for patient education in a UK consultation setting.
References
University of Manchester. Fears over ‘life-saving' drug unfounded, finds review. Available at: https://www.manchester.ac.uk/about/news/fears-over-life-saving-drug-unfounded-finds-review/
Krupitsky E, Zvartau E, Woody G, et al. Naltrexone for heroin dependence. Available at: https://pmc.ncbi.nlm.nih.gov/articles/PMC6353110/
O'Brien CP, et al. Naltrexone trial and broader evidence discussion. Available at: https://pmc.ncbi.nlm.nih.gov/articles/PMC2565602/
Younger J, Parkitny L, McLain D. Low-dose naltrexone for fibromyalgia and other conditions. Available at: https://pmc.ncbi.nlm.nih.gov/articles/PMC3962576/
Lee JD, et al. Safety, contraindications, and overdose risks with naltrexone. Available at: https://pmc.ncbi.nlm.nih.gov/articles/PMC6332608/
NEJM. Naltrexone in alcohol dependence study. Available at: https://www.nejm.org/doi/full/10.1056/NEJMoa011127
If you're weighing naltrexone or low-dose naltrexone, a supervised review can help you work out whether it fits your goals and your safety profile. Visit Courier Pharmacy to read more about prescriber-led options, check whether a consultation is suitable, and take the next step with clear medical guidance.


